How the Anion Gap Evaluates
The anion gap is a valuable part of acid-base evaluation because it assists healthcare providers and students see how the main electrolytes interact to one another in the blood. It is not a direct measurement of a one substance. Instead, it is a calculated value derived from routine serum chemistry tests that indicates the equilibrium between measured cations and measured anions.
In practical terms, the anion gap helps identify whether a patient has an acid-base disorder, especially metabolic acidosis. When the body retains acids or depletes bicarbonate, the chemistry panel changes in consistent ways. An elevated or abnormal gap can point toward hidden acids, also called unmeasured anions, that are not directly listed on a standard electrolyte panel.
The most important measured values in this calculation are sodium, chloride, and bicarbonate. Some formulas also include potassium, though many clinical settings omit it for simplicity. Because the result is derived from typical serum electrolytes and other blood chemistry data, the anion gap serves as a quick diagnostic tool during patient assessment.
An Anion Gap Calculator makes it easier to calculate anion gap values rapidly and accurately. That can support a clearer understanding of the cause of acidosis, whether the issue is a simple bicarbonate loss, an excess acid load, or another process affecting the body’s acid-base balance.
How to Use the Anion Gap Calculator
To use an Anion Gap Calculator, enter the serum values for sodium, chloride, and bicarbonate from the lab results. These values are usually measured in milliequivalents per liter, and the calculator applies the standard formula to calculate the result.
Most calculator tools are designed for quick bedside review or educational use. They allow turn a basic blood chemistry panel into a more meaningful metabolic acidosis evaluation. If you also have the albumin level available, a more advanced calculator may let you correct for albumin and anion gap calculator tool produce a corrected anion gap.
Here is the basic process:
- Input the sodium value from the lab report. Input chloride and bicarbonate values from the same sample if possible. As an option: enter potassium if the calculator includes it. If needed: add albumin if you want a corrected value. Review the result against the expected reference range or normal range.
For precise interpretation, the numbers should come from the same blood draw whenever possible. Changes in timing, fluid status, or treatment can affect the result. The calculator is most useful when paired with the rest of the clinical picture rather than used as a standalone answer.
Anion Gap Formula and Computing Steps
The most widely used anion gap formula is:
Na minus Cl minus HCO3
In expanded form, the formula becomes:
Anion gap = sodium - chloride - bicarbonate
Some practitioners include potassium in the equation:
Anion gap = sodium + potassium - chloride - bicarbonate
This version may produce a marginally higher result, but both formulas are used in practice. The key is to know which method the calculator is using so the interpretation matches the calculation.
To calculate the value one step at a time:
- Begin with the sodium value. Take away chloride. Subtract bicarbonate. If potassium is part of the formula, enter potassium before subtracting chloride and bicarbonate.
Calculation example: If sodium is 140, chloride equals 102, and bicarbonate is 24, the calculation would be 140 - 102 - 24 = 14. If potassium is included at 4 as well, then 140 + 4 - 102 - 24 = 18.
This simple arithmetic can help identify an elevated anion gap, but interpretation depends on the lab’s procedures and the patient’s overall status. A result that seems abnormal should always be considered in the setting of clinical symptoms, medications, and other lab results.
Normal Anion Gap vs High Anion Gap
A normal anion gap usually suggests that the balance between measured cations and anions is in the expected reference range. That does not automatically imply the patient is normal, but it may imply that the acidosis, if present, is due to bicarbonate loss rather than accumulation of unmeasured acids.
A high anion gap is more concerning because it often indicates the presence of extra acids in the bloodstream. This pattern is classically seen in high anion gap metabolic acidosis, where acids increase and bicarbonate decreases as the body tries to neutralize the acid load.
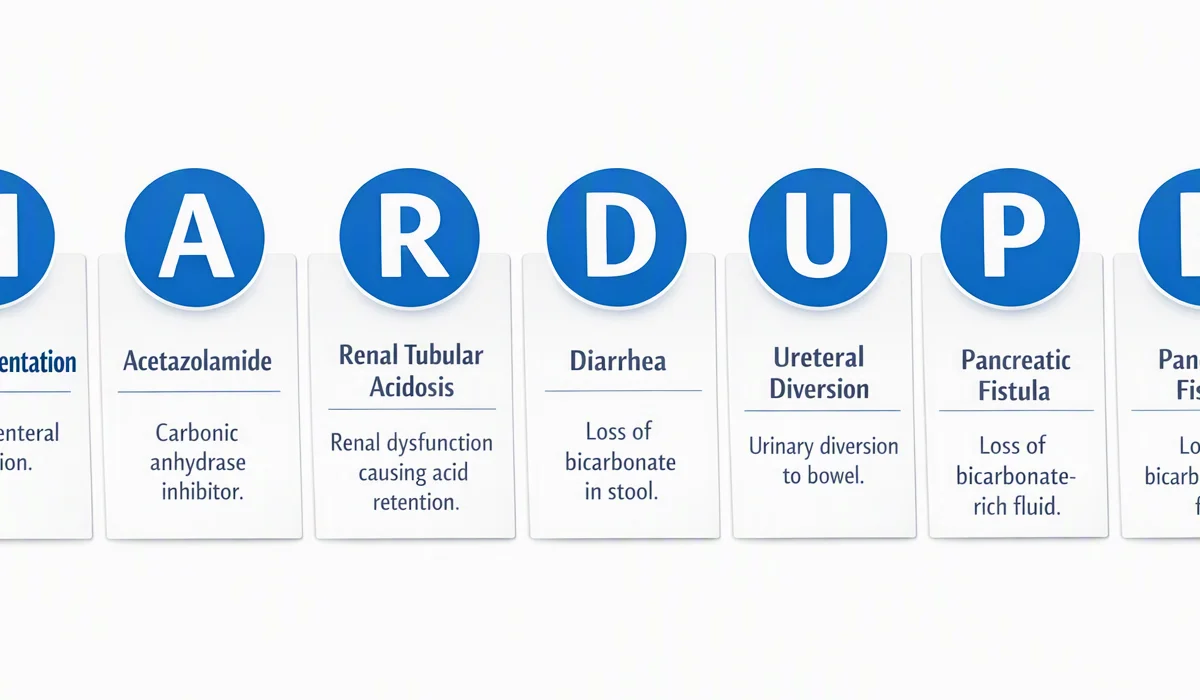
Grasping the difference is central to metabolic acidosis workup. A normal gap can be associated with loose stools, renal tubular issues, or bicarbonate loss. A high gap more often suggests hidden acid accumulation from conditions such as lactic acidosis, ketoacidosis, or kidney-related causes.
The anion gap is not a diagnosis by itself. It is a clue. The result should guide additional testing and support broader clinical reasoning rather than replace it.
Corrected Anion Gap & Albumin Correction
Albumin is a major unmeasured anion in blood, so decreased albumin can make the measured gap look reduced than it really is. This is why many of the clinicians use a corrected anion gap when hypoalbuminemia is present.
If albumin is decreased, the usual gap may underestimate the severity of an acid-base problem. In that situation, the calculator may correct for albumin to better reflect the underlying chemistry. This adjustment is especially helpful when interpreting lab results in very sick patients or anyone with low protein levels.
Why does this matter? A patient can appear to have a typical anion gap even when excess acids are present if albumin is low enough. The corrected result can reveal a hidden high anion gap that would otherwise be missed.
Albumin adjustment improves clinical interpretation because it accounts for one of the key contributors to the body’s electrical balance. In practice, corrected values are often more useful than the raw number alone, especially when evaluating suspected acid-base disturbances.
Common Causes of Elevated Anion Gap
An elevated anion gap often indicates that the body has accumulated acids or other unmeasured particles. Various conditions are traditionally associated with this pattern, and spotting them helps pinpoint the reason for acidosis.
Lactic acid buildup is a leading cause. It occurs when lactate builds up due to poor oxygen delivery, shock, severe illness, or other stressed conditions. Because lactate is an unmeasured anion, it raises the gap.
Ketone-related acidosis is another key cause. This may occur in diabetes, starvation, or alcohol-related states, where ketone bodies collect and disrupt the acid-base balance.
Uremic buildup from reduced kidney function is also important. In severe advanced kidney dysfunction, acids are not cleared effectively, and retained toxins add to a higher gap.
Other causes can include toxins, medications, and metabolic conditions that raise acid production or reduce acid removal. The main point is that a high gap should prompt a search for occult acid production or reduced removal rather than a narrow focus on the number itself.
How to Interpret Results in Clinical Context
Assessing the anion gap correctly requires far more than a number. A good clinical interpretation brings together the gap with signs, vital signs, history, medications, and other lab values such as an arterial blood gas.
The arterial blood gas helps show whether the patient actually has low pH or alkalosis, whether compensation is occurring, and whether the primary disorder aligns with the chemistry panel. The anion gap then adds another layer by identifying whether the metabolic problem is likely due to extra acids or bicarbonate loss.
The delta gap is also helpful in more complex cases. It contrasts the change in the anion gap with the change in bicarbonate to look for mixed disorders. For example, a patient may have high gap metabolic acidosis along with a separate metabolic alkalosis or a concurrent normal gap acidosis.
This is why the Anion Gap Calculator is best used as part of a broader workflow. It supports decision-making, but the final interpretation should combine the complete acid-base picture, including the patient’s clinical status and any possible base deficit.
Limitations of Anion Gap Calculation
Although the anion gap is important, it has several limitations. One issue is lab variation. Different instruments, assay methods, and reporting practices can produce slightly different results, which means the reference range may differ by laboratory.
Another limitation is that the gap only reflects measured and unmeasured anions indirectly. It does not identify the specific acid responsible. A high value may indicate a disorder, but it cannot distinguish between lactic acidosis, ketoacidosis, or other causes without additional context.
Electrolyte measurement problems can also affect accuracy. Severe electrolyte disorders, changes in protein concentration, or unusual blood chemistry patterns may distort the result. In addition, the presence of certain ions can change how the gap appears even if the true acid burden has not changed dramatically.
Because of these limits, the anion gap should be used as one part of a complete acid-base disorder review. It remains a strong clue, but not a definitive answer. The ideal use of the calculator is to guide thoughtful interpretation of lab results, not to substitute for clinical reasoning.
FAQ About the Anion Gap Calculator
What is an anion gap calculator used for?
An Anion Gap Calculator is used to calculate anion gap values from routine lab results and support acid-base evaluation. It is especially helpful in metabolic acidosis evaluation because it can assist in identifying whether the problem is related to hidden acids, bicarbonate loss, or another acid-base disorder.
What is the normal anion gap range?
The reference range for the normal anion gap varies by laboratory and by whether potassium is included in the formula. In general, many labs consider a value in the low to mid-teens to be normal, but the exact range should always be interpreted using the reporting lab’s stated normal range.
How do you calculate the anion gap from lab values?
Use the standard anion gap formula: sodium - chloride - bicarbonate. Some versions add potassium before subtracting chloride and bicarbonate. The calculator performs this step automatically using the provided serum electrolytes, making it easier to review blood chemistry results quickly.
Why do you correct the anion gap for albumin?
You correct for albumin because low albumin can mask a true gap elevation. In hypoalbuminemia, the measured value may look normal even when unmeasured acids are present. A corrected anion gap gives a more accurate picture of the patient’s acid-base status.
What conditions cause a high anion gap?
Common causes of a high anion gap include lactic acidosis, ketoacidosis, and uremia. Severe renal failure, toxins, and other causes of retained acids can also cause an elevated value. The result should always be reviewed in the context of the full clinical picture and any associated arterial blood gas findings.