What Anion Gap Measurement Shows
The anion gap is a useful way to interpret serum chemistry results and assess the difference between measured cations and measured anions in the body. It is frequently used alongside an electrolyte panel to spot an electrolyte imbalance or an underlying acid-base disorder. While it is not a diagnosis by itself, it is a valuable screening tool for clinical assessment and patient evaluation.
In simple terms, the anion gap reflects the difference between the positively charged and negatively charged components that are routinely measured in serum electrolytes. The main values involved are sodium, chloride, and bicarbonate, with potassium sometimes included depending on the formula used. Because many important acids are not directly measured in routine testing, the anion gap helps indicate the presence of unmeasured anions that may be contributing to a metabolic disturbance.
Clinically, this measurement has important significance in the evaluation of metabolic acidosis. It can point toward a wide differential diagnosis, especially when paired with a blood gas and the rest of the serum chemistry profile. Used correctly, it supports diagnostic reasoning rather than replacing it.
Using an Anion Gap Calculator
An Anion Gap Calculator delivers a fast calculation from frequently reported serum values. Provide the patient’s sodium, chloride, and bicarbonate from the laboratory result, and the calculator returns the anion gap. Some calculators also support inclusion of potassium, though the standard approach often omits it for simplicity and alignment with many clinical workflows.
The basic process is simple:
- Check the patient’s electrolyte panel and ensure the relevant serum values. Add sodium, chloride, and bicarbonate into the calculator. Examine the calculated result in the context of the clinical presentation. Consider whether albumin may require an adjustment. Use the result as part of broader interpretation, not as a stand-alone answer.
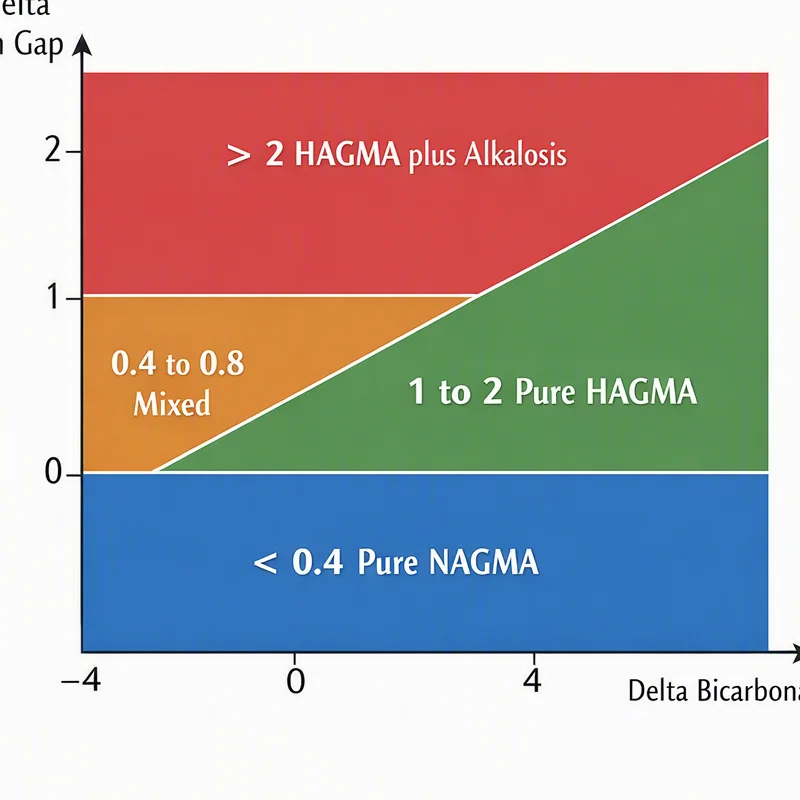
This calculation can be especially helpful when assessing whether a metabolic disturbance is consistent with high anion gap metabolic acidosis or normal anion gap metabolic acidosis. In practice, the number is only one part of the analysis. The real value of the calculator is in helping clinicians efficiently connect chemistry data to acid-base balance and the likely mechanism of disease.
Because the calculation is based on routine serum values, the quality of the input matters. If there is a measurement issue, missing data, or a specimen concern, the output may be misleading. A calculator is a screening tool, but the interpretation still depends on clinical judgment.
Anion Gap Formula and Reference Range
The standard anion gap formula is:
Anion gap = sodium − (chloride + bicarbonate)
Some clinicians include potassium in the calculation, but the streamlined version above is frequently used because potassium has a small effect to the overall result. Whatever the exact formula, the goal is the same: to estimate the difference between measured ions and identify the presence of unmeasured anions.
The normal anion gap depends on the laboratory and the method used, so it is important to check the local reference range. A reported result should always be compared with the range provided by the lab rather than assumed to be normal or abnormal based on a single universal cutoff. Differences in analyzer technology, reporting conventions, and whether potassium is included can all influence the expected interval.
Because of this variability, clinicians should read the result as part of the broader serum chemistry profile. The most useful approach is to compare the calculated gap with the lab’s reference range, then decide whether the result is elevated, lowered, or within range. That interpretation has direct clinical significance in acid-base analysis.
Origins of a Elevated Anion Gap
A high anion gap metabolic acidosis suggests the accumulation of acids that are not directly measured in routine serum chemistry. This finding often indicates that the body is producing excess acid, depleting bicarbonate in the process and leaving behind undetected anions. The result is a greater-than-expected calculated gap.
One common cause is lactic acidosis, in which lactate builds up during tissue hypoperfusion, severe illness, hypoxia, or other metabolic stress. Another important cause is a ketone-driven acidosis, which may occur in diabetes, starvation, or alcohol-related metabolic disturbance. In these settings, ketone bodies drive the elevated gap and the associated acid-base disorder.
Impaired kidney function is also a classic cause. As kidney function declines, the body becomes less able to clear acids efficiently, and retained solutes lead to the widening gap. Other causes may exist, but these three are among the most clinically important because they are common and often urgent.
When the anion gap is elevated, interpretation should focus on the context of the patient’s symptoms, serum values, and blood gas findings. The calculator helps support the presence of a metabolic pattern, but the differential diagnosis still depends on the overall clinical picture. An elevated gap is a warning to look for a significant acid load, impaired clearance, or both.
Reasons of a Typical or Decreased Anion Gap
A normal anion gap metabolic acidosis can still reflect a real acid base imbalance, even though the calculated gap is not elevated. In these cases, bicarbonate is usually depleted, and chloride increases to maintain electrical neutrality. This pattern is often called chloride-rich metabolic acidosis and may occur with gastrointestinal bicarbonate loss, renal tubular problems, or certain medication effects.
A lowered result may also occur with hypoalbuminemia. Because albumin has negative charge, a reduction in albumin decreases the measured gap. This is one of the most important reasons not to overinterpret a low or normal value without checking protein status and considering a correction.
Paraproteinemia can also alter the result. In some plasma cell disorders, positively charged proteins affect with the balance of measured ions and can reduce the observed gap. This makes the interpretation harder and increases the need for a detailed differential diagnosis.
Other contributors may include laboratory issues, unusual ion composition, or specific medications. The key point is that a normal or low value does not automatically exclude metabolic acidosis. It may instead point to a different pattern of acid-base balance or to a factor that is masking the true burden of acid.
Correcting Albumin and Why It Is Important
Albumin adjustment is crucial when interpreting the anion gap in patients with low protein levels. Because serum albumin is a major unmeasured anion, a decrease in albumin can cause the calculated gap appear falsely normal or only mildly elevated. That is, the raw number may miss the true acid burden.
The corrected anion gap updates the measured value upward based on the level of hypoalbuminemia. This adjustment strengthens clinical assessment and helps avoid missing a high-gap process in patients whose albumin is decreased. The exact adjustment method may vary by institution, but the principle is the same: lower albumin means a lower baseline gap, so the measured result should be interpreted in light of that change.
This matters most in patients with severe illness, malnutrition, liver disease, nephrotic-range protein loss, or other states associated with low albumin. In those situations, a seemingly normal serum chemistry result may hide a major metabolic disturbance. Albumin correction is therefore not a minor technical detail; it is a key part of accurate interpretation.
For practical use, the calculator output should be considered together with the albumin level whenever available. If albumin is reduced, the adjusted interpretation may reveal a more clinically important acid-base disorder than the uncorrected value suggests.
Medical Assessment in Acid-Base Disorders
The anion gap is most helpful when integrated into the larger assessment of acid-base disorders. A patient with metabolic acidemia should be reviewed using the blood chemistry, the arterial blood gas, and the overall presentation. The gap helps separate between results that suggest acid increase and patterns that suggest bicarbonate loss with compensatory chloride retention.
A blood gas provides important information about pH, carbon dioxide, and respiratory compensation. Along with lab artifact low AG with serum electrolytes, it helps determine whether the primary problem is chemically related, respiratory, or mixed. In this setting, the anion gap is a diagnostic bridge between the chemistry panel and the physiologic response.
For example, a patient with a reduced bicarbonate and elevated gap likely has a high anion gap metabolic process such as lactic acidosis or ketoacidosis. A patient with low bicarbonate but a normal gap may have normal gap metabolic acidosis instead. That distinction changes the evaluation path and often the urgency of care.
Clinical significance also depends on whether the result is unchanged, getting worse, or changing after treatment. Serial measurements can help track response and support patient evaluation over time. The calculation is not only about identifying a problem; it is also useful for monitoring a known metabolic disturbance.
Common Computational Errors and Problems
Even a practical formula can confuse if the base test values are incorrect or insufficient. Measurement mistake is one of the commonest issues. A specimen that is damaged, polluted, delayed, or generally compromised can change serum values and warp the end result.
Another common issue is overlooking that the gap reflects only measured ions. Significant contributors may be hidden as unmeasured anions, so a seemingly normal value does not always mean the chemistry is comforting. The interpretation must include the possibility of overlapping disorders, unusual toxins, or altered physiology.
Providers should also be careful about inconsistent use of the formula. If a calculator includes potassium while another does not, the result may vary somewhat. That is not necessarily an error, but it does mean the reported value must be interpreted according to the exact formula used. Likewise, the normal range should be taken from the same laboratory that produced the result.
Lastly, it is important not to treat the calculator output as conclusive on its own. An anion gap is a first step for analysis, not the conclusive diagnosis. If the clinical picture and the serum chemistry do not match, the discrepancy should lead to a deeper review of the patient’s acid-base balance, medications, renal function, and overall presentation.
FAQ About Anion Gap Interpretation
What is the anion gap in serum chemistry?
The anion gap is a computed value from blood chemistry that helps assess the balance between measured cations and anions. It is commonly used to assess acid-base balance, identify metabolic acidosis, and look for the presence of nonmeasured anions that are not listed on a routine electrolyte panel.
How do you calculate the anion gap?
The most common formula is sodium minus the sum of chloride and bicarbonate. Some formulas also include potassium, but many clinical settings use the simplified version. An Anion Gap Calculator does this calculation mechanically from the reported serum values.
What is the meaning of a high anion gap?
A raised result often indicates high anion gap metabolic acidosis, which indicates acids are accumulating in the body. Typical causes include lactic acidosis, ketoacidosis, and renal failure. The finding should be interpreted alongside the blood gas, symptoms, and other laboratory data.
Why do you correct the anion gap for albumin?
You make this correction because albumin is a major unmeasured anion. When hypoalbuminemia is present, the measured gap may appear falsely low or normal. Albumin correction helps show the more accurate corrected anion gap and supports clinical interpretation.
Can a normal anion gap still indicate metabolic acidosis?
Yes. A normal anion gap metabolic acidosis is a real acid-base disorder and does not rule out acidosis. It often suggests bicarbonate loss with compensatory chloride increase. The full assessment should include serum electrolytes, blood gas analysis, and the clinical context.