What the Anion Gap Measures
The anion gap is a useful way to assess the balance between measured cations and measured anions in the blood. It is commonly used as part of a serum chemistry or an electrolyte panel to help spot an electrolyte imbalance and support clinical interpretation of acid-base disorders. In simple terms, the calculation examines serum sodium against serum chloride and bicarbonate to estimate whether unmeasured acids may be present.
An anion gap calculator is a valuable diagnostic tool because it helps turn raw laboratory values into an actionable calculated value. That value can point to a hidden metabolic derangement, especially when a patient is in an acidotic state. The result does not stand alone; instead, it provides an interpretation framework that includes symptoms, laboratory context, and blood gas findings.
The core idea behind the anion gap is that plasma must remain electrically neutral. If sodium is higher than what chloride and bicarbonate account for, the remaining difference reflects unmeasured ions such as lactate, ketones, or retained acids. This is why the anion gap is so important for recognizing hidden acidosis and other disturbances that may not be obvious from pH alone.
How to Use an Anion Gap Calculator
An anion gap calculator generally asks for the patient’s serum sodium, serum chloride, bicarbonate, and sometimes serum albumin. Many calculators can also incorporate albumin correction to deliver a more accurate corrected anion gap. Because albumin is a major unmeasured anion, low albumin can make the gap look deceptively normal.
The usual calculation formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Using this formula, the calculator returns a calculated value that can be compared with the typical reference interval. If the value is elevated, that points to anion gap elevation and raises concern for high-gap metabolic processes. If the value is normal but acidosis is present, a different pattern may be present, such as hyperchloremic acidosis.
When using the calculator, enter in the same chemistry values used in the lab report. If serum albumin is available, apply albumin correction so the result shows the true acid-base picture. This matters especially in critically ill patients, where low albumin can mask a significant acid load.
A helpful practical approach is to check the anion gap after examining the serum chemistry, then compare it with blood gas results. This gives a more complete clinical interpretation than either test alone. In other words, the calculator is especially helpful when it is part of a broader bedside assessment rather than a standalone number.
Blood Gas Analysis and Interpretation of Acid-Base Status
Blood gas interpretation provides important perspective to the anion gap by revealing the patient’s pH, carbon dioxide partial pressure, and bicarbonate balance. An arterial blood gas is often used to assess oxygenation and ventilation as well as acid-base balance, while a venous blood gas can still be useful for pH and carbon dioxide trends in many clinical settings. Each test can support interpretation, but they should be read with awareness of their distinct features.
The pH shows you whether the patient is acidemic or alkalemic. The CO2 partial pressure helps determine whether the primary process is respiratory or metabolic, and bicarbonate reflects the metabolic component. If the pH is low and bicarbonate is low, the pattern often points toward metabolic acidosis. If carbon dioxide is also low, that may suggest respiratory compensation as the body attempts to offset the acid load.
Blood gas analysis becomes especially useful when paired with the anion gap. A low pH with low bicarbonate and elevated anion gap strongly suggests a high-gap acid load. A low pH with low bicarbonate but normal anion gap may instead suggest bicarbonate loss. This combination of findings allows a more precise acid-base diagnosis and prevents overreliance on a single calculated number.
It is also necessary to consider whether the blood gas is showing a primary metabolic problem, a primary respiratory problem, or a mixed disorder. The pH provides the overall direction, while the partial pressure of carbon dioxide helps determine whether the lungs are compensating appropriately. That relationship is key to meaningful clinical interpretation.
Rules, Expected Values, and Corrections
The usual anion gap formula is straightforward, but the interpretation is more subtle. Most labs calculate with sodium minus chloride and bicarbonate, though some include potassium. Because potassium is usually a minor contributor, many clinicians favor the basic version. What matters most is uniformity and knowing which reference interval is used to the lab method being used.
The reference range for the anion gap differs by laboratory analyzer and local reporting standards. A typical normal anion gap is often in the low to mid teens, but the exact range depends on the assay and whether potassium is included. That is why the number should always be interpreted in the context of the lab’s own reference interval rather than an assumed universal cutoff.
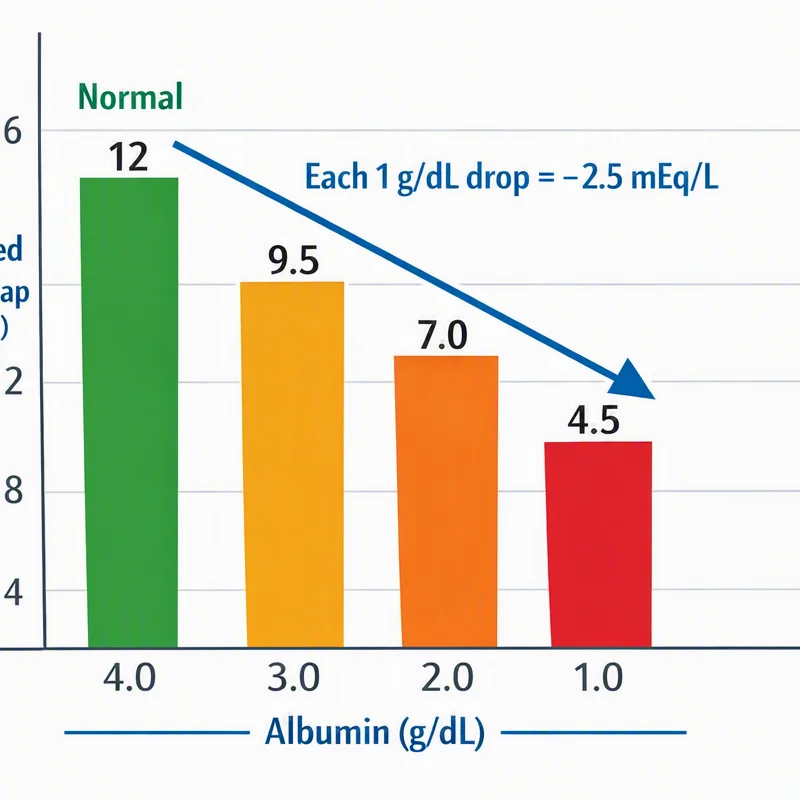
Albumin correction is essential when serum albumin is low. Because albumin is a major unmeasured anion, hypoalbuminemia lowers the expected anion gap. Without correction, a patient may appear to have a normal value even though a significant acid burden is present. The result is a more accurate corrected anion gap, which is particularly helpful in patients with chronic illness, inflammation, or fluid shifts.
The key practical lesson is that the anion gap should not be interpreted in isolation. The number is best viewed together with bicarbonate, pH, and carbon dioxide as part of a broader acid-base assessment. That integrated approach enhances confidence and reduces the risk of missing a clinically important metabolic disorder.
Increased Anion Gap Metabolic Acidosis
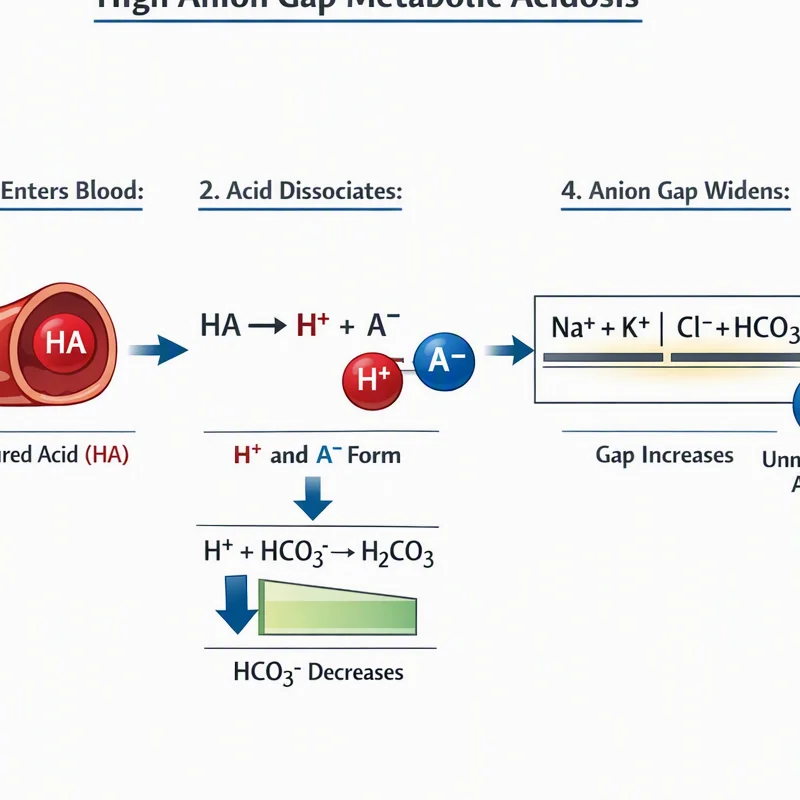
Elevated anion gap metabolic acidosis happens when acidic substances build up in the bloodstream. This is one of the key patterns detected by the anion gap because it can identify severe disease early. In many cases, the anion gap is raised before the complete clinical picture becomes obvious, making it a valuable marker of developing metabolic acidosis.
Typical causes include lactic acidosis, ketoacidosis, and uremia. Lactic acidosis can develop when tissue perfusion is impaired or oxygen utilization is disrupted, leading to lactate accumulation. Ketoacidosis occurs when ketones build up, often in states of insulin deficiency or prolonged starvation. Uremia reflects retention of acids and other waste products when kidney function is severely reduced.
From an interpretation standpoint, a high-gap disorder often produces a reduced bicarbonate level and a decreased pH. The respiratory system may respond by lowering the partial pressure of carbon dioxide through increased ventilation. That compensation can somewhat lessen acidemia, but it does not remove the underlying metabolic problem. This is why using blood gas analysis alongside the anion gap strengthens diagnostic accuracy.
High-gap metabolic acidosis can also coexist with other acid-base disorders. For example, a patient may have a high-gap process and a simultaneous metabolic alkalosis or respiratory disorder. In these cases, the anion gap calculator is a starting point, not the final answer. Careful review of the overall acid-base balance is required to avoid missing a mixed disorder.
Standard Anion Gap Metabolic Acidosis
Normal anion gap metabolic acidosis is also called chloride-rich acidosis. With this pattern, bicarbonate falls but chloride rises enough to keep the overall gap within the expected reference interval. This finding may still reflect a significant acid-base problem even though the anion gap itself https://anion-gap-tool752.lowescouponn.com/anion-gap-calculator-and-interpretation-reference is not elevated.
A frequent mechanism is bicarbonate loss. The body becomes depleted of base, and chloride increases as a compensatory change. This can occur with gastrointestinal losses such as diarrhea, where bicarbonate-rich fluid is depleted. In the right clinical context, the combination of low bicarbonate and high chloride points toward this pattern rather than a high-gap disorder.
A second major cause is renal tubular acidosis, in which the kidneys fail to properly acidify urine or reclaim bicarbonate. This causes a persistent acidotic state despite a normal anion gap. Since the mechanism is different from high-gap acidosis, the treatment approach may also differ. This is why differentiating these entities matters in clinical interpretation.
Metabolic acidosis with a normal gap is a good example of why the anion gap calculator should be used together with blood gas analysis. A low pH and low bicarbonate may indicate metabolic acidosis, but the anion gap tells you whether the problem is due to unmeasured acids or to bicarbonate loss with chloride retention. This separation is central to the interpretation framework.
Typical Calculation Missteps and Medical Challenges
Several issues can distort the apparent anion gap and lead to misinterpretation. One of the most common is laboratory error, which can arise from specimen handling, analyzer variation, or data entry errors. If the result does not fit the patient’s condition, the chemistry should be rechecked before making big decisions.
Hypoalbuminemia is another common pitfall. Since low albumin lowers the unmeasured anion pool, the anion gap may appear artificially normal. This is one reason albumin-adjusted calculation is so important. Without it, a serious acid load can be missed, especially in admitted or very ill patients.
Calcium ion levels and other electrolyte shifts can also affect the broader acid-base environment. While they do not directly define the anion gap, they may influence the overall clinical picture and contribute to confusion if the analysis focuses only on one number. Careful review of the electrolyte panel helps reduce this risk.
Another major pitfall is relying on the anion gap without considering pH and carbon dioxide. A calculated value may be useful, but if the patient has a respiratory disorder or mixed acid-base pattern, the final conclusion can be misleading. Good interpretation uses the anion gap calculator as one component of a larger diagnostic tool, not as a replacement for blood gas analysis.
Finally, reference interval differences between laboratories can produce noticeable differences. A result that seems slightly elevated in one setting may be normal in another depending on the analyzer, method, and reporting conventions. Understanding the local reference range is crucial for accurate clinical interpretation.
Frequently Asked Questions About Anion Gap and Blood Gases
How can you calculate the anion gap from blood gas results?
You generally do not calculate the anion gap from the blood gas alone. The anion gap calculator relies on serum sodium, serum chloride, and bicarbonate from the chemistry panel. Blood gas analysis includes pH and partial pressure of carbon dioxide so you can assess the acid-base disorder in greater detail. If the blood gas reports a bicarbonate value, it can offer context, but the standard calculated value is still based on serum electrolytes.
Which is the normal anion gap range in adults?
The reference range depends on the laboratory technique and whether potassium is included. Many laboratories list a typical anion gap in the mid-teens, but the exact range should always be checked against the local report. The most important step is to check the result with the lab’s own interval rather than using a standard cutoff.
Why do you correct the anion gap for albumin?
Correction for albumin is required because albumin in serum serves as a major unmeasured negatively charged ion. If albumin levels are low, the anion gap may appear falsely normal even when an acid load is present. The albumin-corrected anion gap enhances recognition of occult acidosis and gives a better estimate of the underlying metabolic state.
Is blood gas analysis alone enough to show metabolic acidosis?
Blood gas analysis can often point to metabolic acidosis by revealing a low pH and low bicarbonate, but it does not always reveal the cause. The anion gap helps distinguish between high anion gap metabolic acidosis and normal anion gap metabolic acidosis. Combining both together gives a better clinical interpretation framework than blood gas alone.
What can cause a high anion gap in clinical interpretation?
Common causes include lactic acid buildup, ketone-related acidosis, and uric toxin buildup. Such conditions produce a higher anion gap by bringing undetected acids to the circulation. If the anion gap is high, the result should be read alongside pH, bicarbonate, and carbon dioxide so you can assess the degree of the acid-base disturbance and whether respiratory compensation is present.