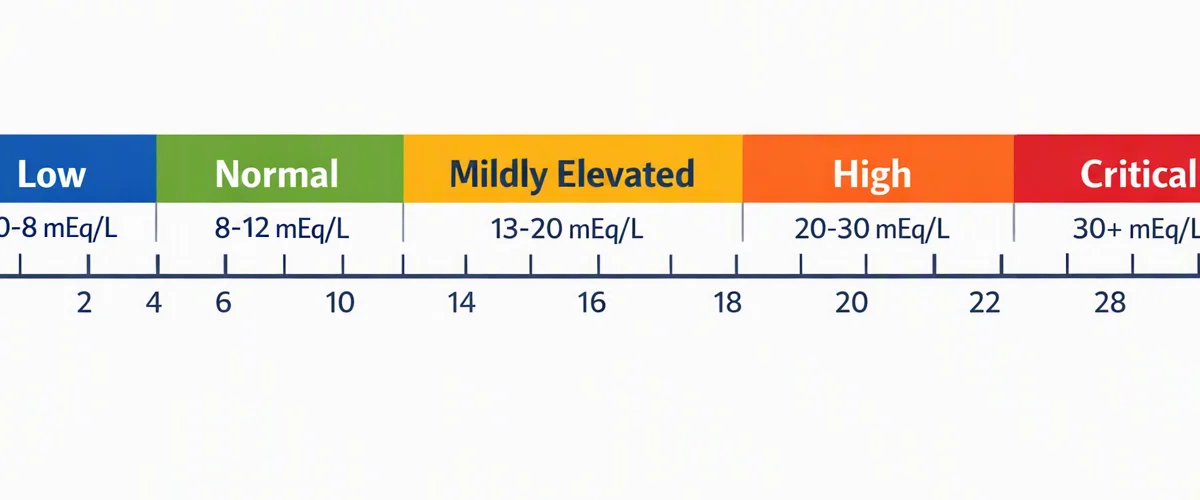
What Anion Gap Means
The anion gap is a practical way to analyze serum electrolytes and understand whether the body’s acid-base status may be disturbed. It is not a straight measurement of a single substance. Instead, it is a derived value that helps identify hidden ions in the blood when examining a standard electrolyte panel.
Clinically, the anion gap is most often used to investigate acid buildup. This is a metabolic issue in which too much acid builds up or too much bicarbonate is lost. Because the calculation uses routine blood test results, it acts as a practical assessment tool in laboratory interpretation and clinical evaluation.
An Anion Gap Calculator helps users calculate anion gap quickly and consistently, especially when they want anion gap with units properly shown. That matters because the value is only meaningful when the reference ranges and context are understood properly.
In basic terms, the anion gap reflects the relationship between positively charged and negatively charged particles in blood. The main electrolytes involved are sodium, chloride, and bicarbonate. When the balance shifts, the result can point toward an electrolyte imbalance, an acid-base disorder, or a more specific condition such as high anion gap metabolic acidosis.
Anion Gap Calculation & Estimation
The usual anion gap equation relies on three common serum measurements: sodium, chloride, and bicarbonate. The formula is:
Anion gap = sodium − (chloride + bicarbonate)
Certain labs may use a slightly different version that includes potassium, but the usual clinical formula is based on serum sodium, serum chloride, and serum bicarbonate. This is the calculation many people expect from an Anion Gap Calculator.
To work out anion gap step-by-step:
- Start with the serum sodium value. Add the serum chloride and serum bicarbonate values together. Remove that total from sodium.
As an example: if sodium is 140, chloride is 102, and bicarbonate is 24, the calculation is 140 − (102 + 24) = 14. This is the fundamental calculation, but interpretation depends on the units, the reference range, and whether albumin correction is needed.
Since anion gap is a computed number rather than a directly measured electrolyte, it should always be interpreted alongside the blood chemistry pattern. A apparently normal number does not always rule out disease, and an abnormal result does not always mean a serious disorder without additional context.
Measurement Units Used in Anion Gap Calculation
Anion gap is typically reported in mEq/L or mmol/L. In practice, these values are typically numerically equivalent for the electrolytes used in the formula, which is why many clinicians and lab reports treat them similarly. However, users should always check the laboratory units shown on the report before making assumptions.
The calculation is based on serum chemistry, so the unit formatting reflects how the laboratory measures the electrolytes. Sodium, chloride, and bicarbonate are often listed as either mEq/L or mmol/L, depending on the analyzer and reporting system.
For most routine interpretation, anion gap with units does not require conversion if all components come from the same lab report. Consistency is the key point. A calculator should use values from the same electrolyte panel and preserve the same units in the final answer.
Here are the practical takeaways:
- mEq/L is frequent in clinical chemistry reporting. mmol/L is also frequently used and often matches the numeric result. Mixed units can lead to errors, especially if a value is copied incorrectly.
When using an Anion Gap Calculator, always confirm the units before reviewing the interpretation. Even though the formula is simple, the reliability of the result depends on accurate blood chemistry data and correct laboratory units.
Typical Anion Gap Range and Reference Values
The typical range for anion gap changes by laboratory because various analyzers and reference methods may yield slightly different results. For this reason you should use the lab’s reference range rather than a one universal number.
In many settings, the anion gap is regarded normal when it falls within a narrow range centered around the low teens, but the exact reference values vary. Some reports also adapt interpretation based on whether potassium is included in the formula. Because of these differences, the numeric result should routinely be compared with the local lab’s published values.
Albumin plays an essential role in the normal range. Since albumin is a major unmeasured anion, a low albumin level can make the anion gap appear reduced than expected. This is why albumin correction may be necessary when interpreting blood test results in patients with low albumin.
The corrected anion gap is often more informative than the raw number when albumin is reduced. This adjustment helps prevent missed recognition of an underlying acid-base disorder. If albumin is low, a seemingly normal anion gap can conceal a real abnormality.
Lab values should always be interpreted in context:
- Use the lab-specific normal range. Determine whether the result is uncorrected or corrected. Review albumin level before drawing conclusions.
High Anion Gap vs Normal Anion Gap Metabolic Acidosis
One of the key applications of the anion gap is distinguishing high anion gap metabolic acidosis from normal anion gap metabolic acidosis. Both are forms of metabolic acidosis, but they arise from varied mechanisms and therefore point to various causes.
In high anion gap metabolic acidosis, extra acids accumulate in the body. These acids are not directly measured in the routine electrolyte panel, so the anion gap rises. Common examples include lactic acidosis, ketoacidosis, renal failure, and toxin ingestion.
In normal anion gap metabolic acidosis, bicarbonate is lost and replaced by chloride, so the gap remains within the expected range. This is often called hyperchloremic metabolic acidosis. The acid-base balance is still abnormal, but the pattern is unlike from high-gap states.
Lactic acidosis is a common cause of high anion gap metabolic acidosis. It can occur when tissues are not receiving enough oxygen or when metabolism is greatly stressed. Ketoacidosis is another classic cause, especially when the body produces too many ketones. Renal failure can also cause build-up of acids because the kidneys cannot remove them efficiently.
By contrast, normal anion gap metabolic acidosis is often associated with bicarbonate loss from the gastrointestinal tract or kidneys. The chloride shift anion gap clinical significance helps keep electrical neutrality, so the gap may seem normal even though the patient has a serious acid-base disorder.
Frequent Causes of an Atypical Anion Gap
An abnormal anion gap can indicate several significant clinical issues, but the significance depends on whether the result is elevated or low. For clinical practice, the most relevant abnormality is a raised result.
Ketone-related acidosis is a common cause of increased anion gap. This may arise in diabetes, starvation, or other metabolic states where ketone production goes up. These acids increase the gap because they add unmeasured anions to the bloodstream.
Impaired kidney function can also raise the anion gap by impairing acid excretion. As kidney function declines, acids accumulate, and the calculated gap increases.
Poisoning is another significant cause. Certain toxic substances generate unmeasured acids or interfere with metabolism, leading to high anion gap metabolic acidosis. In clinical evaluation, this possibility should be kept in mind when the blood chemistry pattern is unexpected or extreme.
Elevated lactate acidosis is often seen in sudden illness, poor tissue perfusion, or systemic stress. It is one of the major causes to detect quickly because it may indicate a major underlying problem.
Loss of bicarbonate is more often associated with a normal anion gap state. While the gap may not be elevated, the bicarbonate level is decreased, and the clinical impact can still be significant.
Other possible contributors can include mixed acid-base disorders, medication effects, and changes in serum electrolytes. This is why an increased or low anion gap should never be interpreted in isolation.
How to Understand Results Properly
Accurate interpretation involves more than checking a value against the reference range. A thoughtful clinical interpretation should account for albumin, the electrolyte balance, and the probable acid-base disorder.
First, consider albumin correction if the patient has low albumin. As albumin influences the anion gap, reduced levels can hide a clinically relevant elevation. The corrected anion gap provides a better estimate of the true acid-base status in many cases.
Then, look for a chloride shift. If bicarbonate is low and chloride is high, the pattern may indicate normal anion gap metabolic acidosis. That does not rule out illness; it just suggests a different mechanism than high-gap states.
Third, connect the result with the broader acid-base disorder. The anion gap is one part of the story. It should be interpreted with pH, bicarbonate, clinical symptoms, and other laboratory interpretation details when available.
A useful approach is to think in layers:
- Is the anion gap high, normal, or low? Are sodium, chloride, and bicarbonate consistent with one another? Is albumin low enough to require correction? Does the overall pattern match the patient’s presentation?
Using this approach helps reduce common errors in interpretation. A result should reinforce the diagnosis, not override clinical judgment.
When to Use an Anion Gap Calculator
This Anion Gap Calculator is most useful whenever you have laboratory values from an electrolyte panel and want a quick, accurate way to calculate the anion gap. It is especially helpful during a medical assessment when rapid blood chemistry https://anion-gap-range628.lumenforgex.com/posts/anion-gap-calculator-for-evaluating-metabolic-alkalosis-review review is needed.
Use a calculator when reviewing lab values that include sodium, chloride, and bicarbonate. These measurements are usually available in a standard electrolyte panel and can be entered directly without manual arithmetic errors.
A calculator is also useful when comparing multiple sets of blood test results over time. Trend analysis can reveal whether the gap is rising, decreasing, or remaining stable. That can be useful in monitoring treatment response or identifying a worsening metabolic disturbance.
In clinical workflows, the calculator serves as a practical support tool for laboratory interpretation. It can help healthcare providers, students, and patients understand the relationship between serum electrolytes and acid-base balance. It is not a substitute for professional diagnosis, but it can improve clarity when reviewing blood chemistry results.
It is worth using when:
- Evaluating possible metabolic acidosis Checking for high anion gap metabolic acidosis Reviewing low albumin and thinking about albumin correction Reviewing an unexplained electrolyte imbalance
Frequently Asked Questions
What is the formula for calculating anion gap?
The standard formula is sodium minus the sum of chloride and bicarbonate. In equation form, it is anion gap = sodium − (chloride + bicarbonate). This is the most common formula used by an Anion Gap Calculator.
What units are used for anion gap?
Anion gap is commonly reported in mEq/L or mmol/L. In many cases, the numeric result is the same in both formats, but you should always follow the laboratory units shown on the report.
What is a normal anion gap range?
The normal range depends on the laboratory reference range and the testing method used. Always compare the result with the local reference values rather than assuming one universal normal range.
How does low albumin affect the anion gap?
Reduced albumin can decrease the observed anion gap because albumin is a key not directly measured anion. This is why albumin correction is important; the adjusted anion gap may uncover an issue that the uncorrected value hides.
What does a high anion gap indicate?
A high anion gap often suggests high anion gap metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxin ingestion. The result should always be read with the full clinical picture and other blood test results.