What the anion gap indicates
The anion gap is a calculated value used to help interpret serum electrolytes and spot hidden acids in the blood. It is based mainly on the measured levels of sodium, chloride, and bicarbonate-related chemistry, and it gives clinicians a fast clue about acid-base balance. A above-normal result can point to an underlying metabolic derangement, while a normal result may suggest a different process altogether.
In basic terms, the anion gap reflects the difference between the main positively charged and negatively charged particles reported on a basic chemistry panel. Because many clinically important acids are not directly measured, the gap can act as a biochemical marker for their presence. This is why it is important in evaluating metabolic acidosis and other forms of acid-base disturbance.
The most common formula uses sodium minus the sum of chloride and bicarbonate. Since chloride is usually measured alongside sodium, any change in these values affects the calculated gap. That makes the anion gap a useful tool in emergency assessment and diagnostic workup, especially when clinicians are trying to distinguish a high anion gap metabolic acidosis from a normal anion gap pattern.
How an Anion Gap Calculator is used in medical assessment
An Anion Gap Calculator assists healthcare providers and trainees complete anion gap calculation rapidly and reliably. It is most useful when reviewing a chemistry panel in the setting of possible poisoning, volume depletion, renal injury, or unexplained acid-base changes. The calculator does not diagnose a condition on its own, but it aids lab interpretation and helps determine whether additional testing is needed.
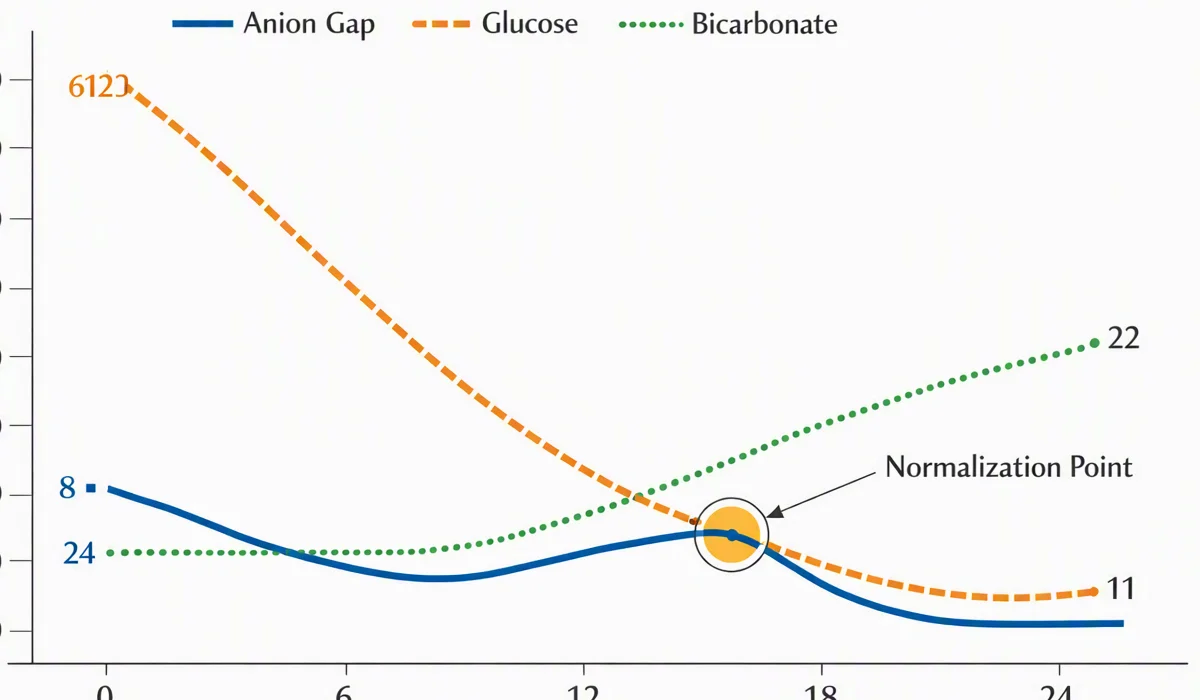
One important detail in clinical interpretation is the role of bicarbonate. When bicarbonate falls, the body may be using it up while buffering excess acid, which can raise suspicion for metabolic acidosis. The calculator can also be adjusted for albumin correction, because low albumin lowers the measured anion gap and can hide a true elevation. This is why an albumin-corrected anion gap is often better calibrated in hospitalized patients or those with chronic illness.
In practice, an elevated result suggests that unmeasured anions such as lactate, ketones, or toxic metabolites may be accumulating. That is where the clinical significance becomes important: the number itself is not the diagnosis, but it can direct the toxicology evaluation and help identify urgent conditions that require treatment.
Can iron overdose increase anion gap?
Absolutely, iron overdose can raise anion gap in some cases. The key issue is not iron as a simple electrolyte abnormality, but the way iron overdose can lead to iron toxicity with systemic injury and acid generation. When the ingestion is serious enough, patients may develop high anion gap metabolic acidosis, often with other dangerous findings.
This is due to the fact that toxic iron can disrupt cellular metabolism, resulting in poor oxygen use, tissue injury, and accumulation of acids. One major contributor is lactic acidosis, which can develop when tissues are underperfused or unable to properly use oxygen. In that setting, the body produces additional lactate and other organic acids, which widen the anion gap.
Iron poisoning is a form of toxic ingestion that may evolve quickly. A child or adult who ingests a large amount of ferrous sulfate or another iron-containing product can go from early gastrointestinal symptoms to serious metabolic abnormalities. Not every exposure causes a measurable gap change, but severe cases often do. This is why clinicians consider the anion gap as part of the broader picture rather than as a standalone test.
Bottom line: iron overdose can elevate the anion gap, especially when it causes metabolic acidosis, lactic acid accumulation, or shock-related tissue hypoperfusion. The degree of elevation depends on the dose, timing, and severity of the poisoning.
How iron toxicity can lead to acid-base imbalances
Ferrous iron is highly toxic in excess because it can drive destructive chemical reactions inside cells. At high concentrations, it causes oxidative stress and leads to cellular injury. The result is a metabolic derangement that can affect various organ systems, including the gastrointestinal tract, liver, cardiovascular system, and central nervous system.
Another key mechanism is mitochondrial dysfunction. Mitochondria are essential for efficient energy production, and when they fail, tissues cannot use oxygen effectively. This can lead to anaerobic metabolism and the buildup of lactate, a well-known cause of elevated anion gap acidosis. In severe poisoning, this may be compounded by shock, which reduces oxygen delivery and increases acid production.
These changes explain why iron toxicity is not just a local stomach problem. It can produce systemic toxicity with acid-base imbalance, electrolyte shifts, and hemodynamic instability. The acid-base pattern may evolve over time, so repeat lab interpretation is often required during the toxicology evaluation.
In suspected iron poisoning, an elevated anion gap is often a clue to deeper systemic injury, not just a lab curiosity.
Common test results seen in iron poisoning
Lab findings in iron poisoning are influenced by the timing, dose, and severity, but multiple tests are especially important. A serum iron level is central to confirming exposure and assessing the severity of acute toxicity. Early after ingestion, this level may rise sharply, though it can shift over time as iron moves into tissues.
An arterial blood gas is often used to evaluate acid-base status and to determine whether metabolic acidosis is present. If the patient has a low bicarbonate with a high anion gap metabolic acidosis, that raises concern about significant toxic ingestion and poor perfusion. The ABG can also help identify respiratory compensation or mixed acid-base disorders.
An electrolyte panel is crucial for checking sodium, chloride, and bicarbonate values and for performing accurate anion gap calculation. Clinicians may also check glucose, because hypoglycemia or stress hyperglycemia can accompany systemic illness and help guide management. In severe cases, additional abnormalities may point toward liver injury, dehydration, or evolving shock.
Because the clinical picture can change quickly, repeated testing is often part of the diagnostic workup. Trend data may reveal a worsening elevated anion gap or improving values after treatment.
Warning signs and danger signs that need immediate attention
Iron toxicity often first shows up as digestive symptoms, but severe illness can worsen rapidly. Early symptoms include vomiting and abdominal pain, sometimes with diarrhea, sluggishness, or blood in the vomit. These toxic symptoms can be an initial indication that a toxic ingestion has occurred.
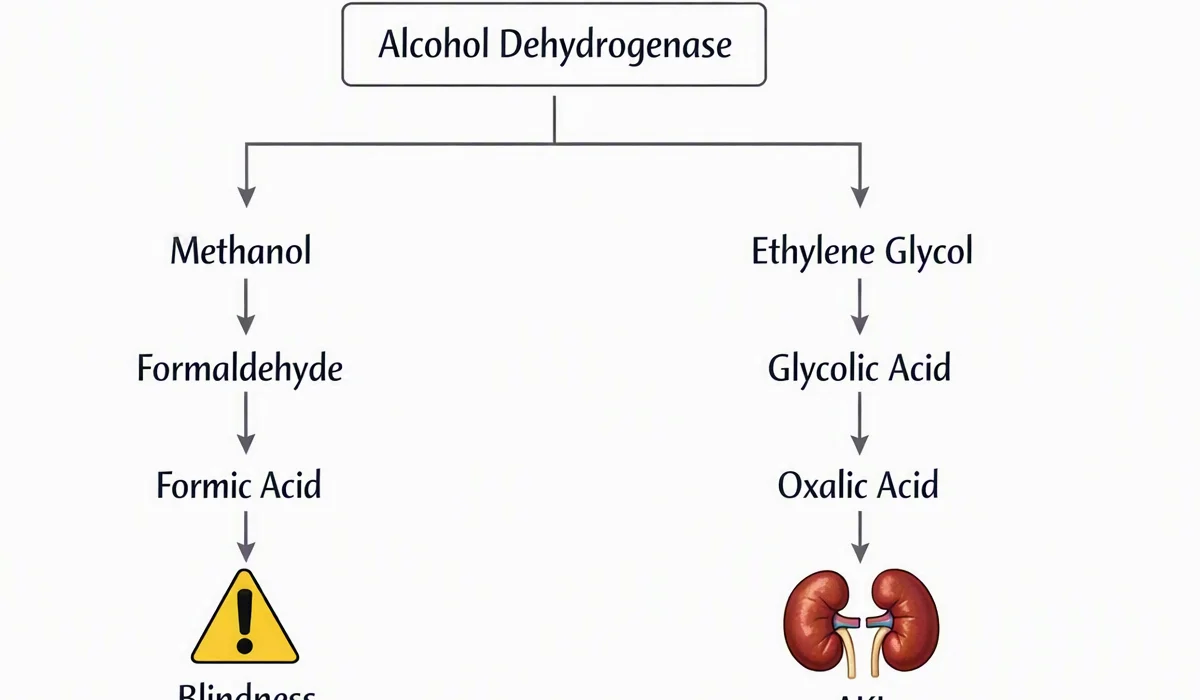
Worrying severe signs include hypotension, altered mental status, and evidence of poor circulation such as cold hands and feet or reduced responsiveness. These signs may indicate worsening systemic toxicity and possible development of shock. When this happens, urgent medical evaluation is needed immediately.
Any person with a possible iron overdose plus ongoing vomiting, abdominal pain, feeling faint, confusion, or collapse should be evaluated urgently. The combination of symptoms and metabolic acidosis can signal a critical condition, especially if the ingestion involved a large amount of ferrous sulfate or a different concentrated iron preparation.
How clinicians evaluate possible iron overdose
Evaluation starts with a careful history of ingestion. Clinicians try to determine what was taken, how much, and whether the product contained elemental iron. The time since ingestion plays https://anion-gap-chart717.evergrovio.com/posts/could-hypoxia-elevate-the-anion-gap a role because it affects both symptom timing and the usefulness of certain tests. Early presentations may have only gastrointestinal symptoms, while later presentations may show metabolic complications.
An electrolyte panel is usually obtained right away to assess sodium, chloride, bicarbonate, and calculate the anion gap. Other tests may include a serum iron concentration, liver studies, kidney function tests, and an arterial blood gas if the patient appears ill or has evidence of metabolic acidosis.
Toxicology consultation is often helpful in significant cases. The diagnostic workup may also include abdominal imaging if tablets are suspected to be present in the gut, especially soon after a large ingestion. Clinicians use the full picture, not just a single number, to decide whether the patient needs observation, decontamination, or antidotal therapy.
Treatment summary for iron toxicity
Care depends on severity, but stabilization comes first. Support measures includes airway protection if needed, monitoring, and treatment of dehydration or shock. Intravenous fluids may be given to restore circulation and improve perfusion, especially if there is hypotension or signs of poor tissue oxygen delivery.
Deferoxamine is the classic antidote used in significant iron toxicity. It binds free iron and helps remove it from the body, reducing ongoing cellular injury. The decision to use it depends on symptoms, serum iron level, acidosis, and evidence of systemic toxicity. In severe cases, it may be lifesaving.
Activated charcoal is generally not effective for iron because it does not bind iron well. That said, management still focuses on urgent decontamination strategies when appropriate, along with close monitoring for worsening metabolic acidosis, electrolyte abnormalities, and hemodynamic instability. The overall goal is to prevent progression to shock and organ failure.
Other causes of an elevated anion gap
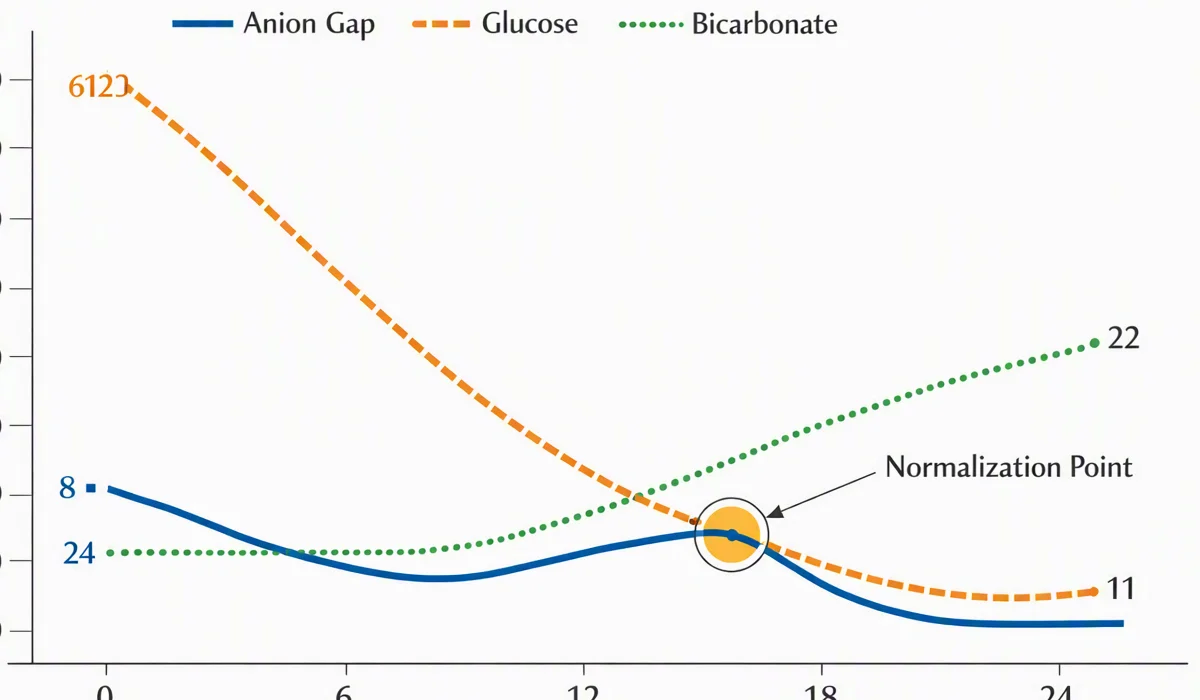
An elevated result on an Anion Gap Calculator does not automatically mean iron toxicity. The differential diagnosis is broad, and clinicians must think through other common causes of acid-base disturbance. Important possibilities include ketone-related acidosis, kidney failure, salicylate poisoning, and systemic infection.
Ketoacidosis can occur in diabetes, starvation, or alcohol-related illness and typically produces organic acids that raise the anion gap. Renal insufficiency can cause retention of acids that are normally excreted. Salicylate poisoning may produce a mixed acid-base picture with an elevated gap. Severe infection can also cause lactic acidosis due to poor perfusion and cellular hypoperfusion.
This is why the lab result must be interpreted in clinical context. A high anion gap supports the presence of acid accumulation, but the cause must be identified through history, symptoms, and targeted testing. In suspected toxic ingestion, clinicians often compare the pattern of electrolytes, glucose, lactate, and serum iron to narrow the diagnosis.
FAQ about iron overdose and anion gap results
Can iron overdose increase anion gap?
Yes. Serious iron overdose can raise the anion gap by causing increased anion gap metabolic acidosis, often through lactic acidosis, shock, and tissue injury. The effect is more likely when the poisoning is major and systemic toxicity is seen.
What type of acidosis is seen with iron toxicity?
Iron toxicity commonly causes high anion gap metabolic acidosis. This happens because of acid buildup from impaired cellular metabolism, lactic acidosis, and poor tissue perfusion. A blood gas and electrolyte panel help verify the pattern.
How can you calculate anion gap correctly?
Anion gap calculation is usually done with sodium minus the sum of chloride and bicarbonate. In some situations, clinicians apply an albumin-corrected anion gap because low albumin can make the gap appear falsely normal. An Anion Gap Calculator helps standardize the calculation.
Will a normal anion gap rule out iron poisoning?
No. A normal anion gap does not rule out iron poisoning, especially early after ingestion or in milder cases. Lab interpretation must include symptoms, timing, serum iron, and the full toxicology evaluation.
What signs suggest an emergency iron overdose?
Emergency symptoms include ongoing vomiting, abdominal pain, hypotension, altered mental status, collapse, or signs of shock. These findings can mean severe iron toxicity and require immediate medical assessment.