What the Anion Gap Means in Excess Iron
The anion gap is a practical way to understand an acid base disorder when a patient has a presumed iron overdose. In toxicology, the anion gap helps clinicians identify whether metabolic acidosis is occurring and whether it may indicate significant systemic toxicity. Because iron poisoning can progress rapidly, the anion gap is often part of the initial emergency assessment alongside the patient’s symptoms and serum electrolytes.
An anion gap calculator is not a diagnosis by itself, but it can help estimate whether the patient has a high anion gap metabolic acidosis, which may point to a dangerous metabolic derangement. In iron toxicity, this finding can support concern for severe poisoning, especially when paired with vomiting, abdominal pain, hypotension, or altered mental status.
From a practical standpoint, the anion gap helps clinicians calculate and interpret the relationship between measured cations and anions in the blood. When the gap rises, it often shows unmeasured acids in the bloodstream. In the setting of iron poisoning, those acids may include lactate from poor tissue perfusion or other metabolites produced during severe toxicity.
It is important to remember that acid-base balance can shift quickly in iron overdose. Early on, a patient may have few laboratory abnormalities, but as toxicity worsens, the anion gap and other laboratory results may change. That is why the anion gap is best used as part of a more comprehensive diagnostic and risk stratification approach rather than as a standalone screening tool.
How to Determine the Anion Gap
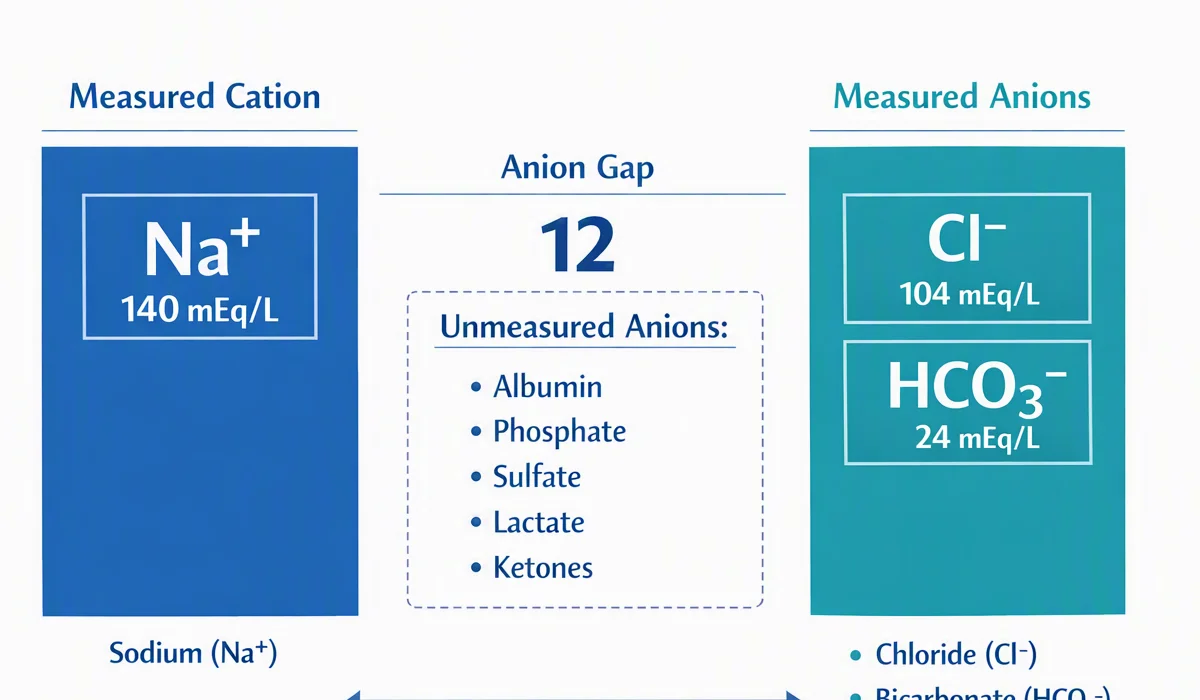
The usual anion gap formula uses three key laboratory values: serum sodium, serum chloride, and serum bicarbonate. The most common version is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
The calculation is straightforward, but it can provide important clinical information in a suspected toxic ingestion. When using an anion gap calculator, the clinician enters the serum sodium, serum chloride, and serum bicarbonate values obtained from the chemistry panel. The result can aid in assessing whether an acid-base disorder is present and whether further toxicology workup is needed.
Normal ranges differ by laboratory, but a clearly elevated gap suggests build-up of unmeasured anions. In iron overdose, that can point toward lactic acidosis or a different severe metabolic disturbance. If the number is only mildly elevated, the result still needs clinical correlation because early iron poisoning can progress over time.
Albumin also matters. Since albumin is a major unmeasured anion, low albumin can make the gap appear falsely normal or lower than expected. In that case, an albumin-corrected anion gap may be more informative. This correction is especially useful when the goal is to interpret laboratory results accurately in the context of emergency assessment and risk stratification.
For example, if a patient has low albumin, the measured anion gap may underestimate the severity of the acid-base disorder. Correcting for albumin helps avoid missing an early clue to significant iron toxicity. In practice, a calculator that includes albumin-corrected anion gap can improve diagnostic precision.
How Iron Toxicity Can Sometimes Elevate the Anion Gap
Iron toxicity can sometimes increase the anion gap because severe poisoning interferes with cellular metabolism and tissue oxygen use. As iron levels climb, the body may develop lactic acidosis, one of the major causes of high anion gap metabolic acidosis in toxic ingestion. Lactate accumulates when cells cannot effectively use oxygen, and that excess acid raises the anion gap.
A key mechanism is cellular hypoperfusion. In significant iron poisoning, fluid loss, shock, and cardiovascular instability can reduce blood flow to tissues. When perfusion drops, cells switch to anaerobic metabolism, generating more lactate. This process can rapidly worsen the acid-base disorder and raise the severity of systemic toxicity.
Another mechanism is oxidative injury. Free iron catalyzes destructive reactions that injure cells and mitochondria. This can disrupt energy https://anion-gap-guide487.theburnward.com/what-is-bicarbonate-s-role-in-the-anion-gap production, impair organ function, and amplify metabolic derangement. The result may be increasing acidosis, rising lactate, and a more elevated anion gap.
In toxicology, the anion gap does not prove iron poisoning on its own, but it can support the clinical suspicion that the patient has a dangerous toxic ingestion. If the calculated gap is elevated and the clinical presentation fits, the clinician should evaluate for iron overdose immediately and monitor for progression. The combination of laboratory abnormalities and symptoms often drives urgency more effectively than any single number.
Key Signs and Medical Red Flags
The clinical course of iron poisoning can progress in phases, and symptoms may show up before the full test picture is clear. Initial warning signs commonly include vomiting and abdominal pain. These symptoms are important because they can reflect direct gastrointestinal injury from iron tablets or liquid formulations.
As toxicity progresses, more serious signs may develop. Hypotension is concerning because it can indicate shock and poor tissue perfusion, both of which can worsen lactic acidosis and raise the anion gap. Persistent low blood pressure should never be dismissed when iron overdose is suspected.
Altered mental status is another critical red flag. Mental confusion, lethargy, agitation, or decreased responsiveness may signal severe systemic toxicity, inadequate perfusion, or worsening metabolic acidosis. When neurologic changes occur, the patient needs urgent reassessment and often escalation to emergency care.
Other symptoms may include diarrhea, dehydration, tachycardia, and signs of worsening illness. However, vomiting, abdominal pain, hypotension, and altered mental status are particularly important because they suggest a higher risk of complications. In an evidence-based approach, these clinical findings should be reviewed alongside laboratory results to guide management and monitoring.
Because iron poisoning can be deceptive early on, a normal appearance does not always mean the ingestion is harmless. The symptom pattern, the estimated dose, and the timing of the toxic ingestion all matter. An anion gap calculator can assist with screening, but it should not replace bedside judgment when there is concern for serious poisoning.
Key Laboratory Tests to Evaluate With the Anion Gap
When using an anion gap calculator in iron overdose, the physician should assess the anion gap along with several other laboratory tests. The clearest iron-related measure is the serum iron level. This value helps gauge the degree of exposure and supports toxicology assessment, especially when drawn at the correct time after ingestion.
Ferritin may also be ordered, although it is not as useful for immediate severity than serum iron. Still, ferritin can add additional information when evaluating iron status and interpreting laboratory results. Another important marker is transferrin saturation, which can reflect how fully transferrin binding capacity has been surpassed by excess iron.
An arterial blood gas is important because it helps assess pH, bicarbonate status, and respiratory compensation. In a patient with likely iron toxicity, the arterial blood gas can determine whether the patient truly has metabolic acidosis and whether there is a mixed acid-base disorder. This is especially important when the chemistry panel and the clinical presentation do not align exactly.
Lactate should also be checked because it often rises in marked iron poisoning. Elevated lactate supports the presence of lactic acidosis from cellular hypoperfusion or mitochondrial dysfunction. When lactate is high and the anion gap is elevated, the combination heightens concern for serious systemic toxicity.
Beyond these tests, clinicians often assess serum electrolytes, kidney function, glucose, and liver tests as part of the overall diagnostic picture. The goal is to judge severity, monitor for complications, and identify whether the patient needs aggressive treatment. In practice, the anion gap is one piece of a larger toxicology assessment.
Drawbacks of the Anion Gap in Iron Overdose
Although the anion gap is valuable, it has significant limitations. A normal anion gap does not necessarily indicate the patient is safe. In initial iron poisoning, the gap may still be normal before acidosis develops. In other cases, the patient may have a mixed acid-base disorder that hides the true severity of the metabolic problem.
For instance, vomiting can produce metabolic alkalosis, which may somewhat counteract metabolic acidosis on paper. This means the calculated anion gap may appear less striking than the clinical picture suggests. That is why clinical correlation is vital. Laboratory results should always be interpreted in the context of symptoms, timing, and the suspected toxic ingestion.
Albumin also affects interpretation. If albumin is low, the measured anion gap may be misleading. An albumin correction or albumin-corrected anion gap can uncover hidden high anion gap metabolic acidosis. This is especially relevant in ill patients, where low albumin is common and the risk of downplaying metabolic derangement is higher.
Another limitation is that the anion gap does not identify the exact cause of acidosis. It can suggest a problem, but it cannot distinguish iron toxicity from other causes of lactic acidosis or intoxication by itself. That is why toxicology decisions should integrate the anion gap with serum iron level, arterial blood gas, lactate, ferritin, transferrin saturation, and bedside findings.
In short, the anion gap is a diagnostic aid, not a definitive answer. It is strongest when used for following trends over time, helping clinicians evaluate whether treatment is working or whether the patient is deteriorating.
If iron overdose Calls for urgent care
Every suspected excess iron ingestion with symptoms or abnormal labs should be treated as time-sensitive. If the patient has emesis, belly pain, dangerously low blood pressure, altered mental status, or signs of metabolic acidosis, prompt escalation is warranted. In these situations, the best next step is to contact the poison center for live guidance and to arrange evaluation in the ER.
Critical care is especially important vital when the anion gap is high, lactate is climbing, or the arterial blood gas shows deteriorating acidosis. These findings can indicate severe iron poisoning and a greater risk of problems. Rapid recognition matters because timely treatment can improve outcomes.
Supportive management is the foundation of acute management. It may involve fluid therapy, shock correction, tracking vital signs, and repeat laboratory testing. When the case shows significant toxicity, chelating therapy may be started, often with deferoxamine as the antidote used in iron poisoning.
Deferoxamine binds free iron and can limit ongoing injury. The choice to use it depends on the patient’s severity, clinical signs, lab results, and toxicology advice. Since treatment thresholds may differ based on the case, poison control involvement is highly valuable for research-backed advice and risk assessment.
Do not delay for the condition to deteriorate if iron poisoning is suspected and the patient is unwell. Severe toxicity can worsen fast, and the exact phrase "Anion Gap Calculator" the anion gap may rise as the patient’s condition deteriorates. Early emergency assessment gives the best opportunity to assess the extent of the overdose, check for complications, and initiate appropriate treatment promptly.
Frequently Asked Questions About Anion Gap and Iron Overdose
How does anion gap help check iron overdose?
The anion gap assists identify whether a patient with likely iron overdose has an acid-base disorder, especially high anion gap metabolic acidosis. In toxicology, that can reinforce concern for significant iron poisoning and prompt more careful monitoring, additional laboratory results, and urgent clinical evaluation.
Can iron overdose cause a high anion gap metabolic acidosis?
Certainly. Iron toxicity can cause lactic acidosis through cellular hypoperfusion, shock, and oxidative injury. As lactate builds up, the anion gap can increase, leading to high anion gap metabolic acidosis. This finding often indicates more severe systemic toxicity.
What lab values should be checked with an anion gap calculator?
At minimum, the calculator uses serum sodium, serum chloride, and serum bicarbonate. In suspected iron poisoning, clinicians should also check albumin, albumin-corrected anion gap, arterial blood gas, lactate, serum iron level, ferritin, and transferrin saturation to better judge severity.
Can a normal anion gap exclude iron poisoning?
It does not. A normal anion gap does not rule out iron poisoning. The patient may be early in the course, or there may be a mixed acid-base disorder or low albumin affecting interpretation. Clinical correlation and toxicology assessment remain crucial.
At what point should someone with suspected iron overdose get emergency care?
Emergency care is needed right away if there is vomiting, abdominal pain, hypotension, altered mental status, or any concern for worsening metabolic acidosis. Poison control should be contacted promptly, and the patient should be evaluated in the emergency department for possible supportive care and chelation therapy with deferoxamine if indicated.