Explaining the Anion Gap?
The anion gap is a derived value that helps assess the balance of electricly charged particles in the blood. It is obtained from routine serum electrolytes and is often used as a clinical indicator in acid-base disorder evaluation. The most common version uses sodium, chloride, and bicarbonate to estimate the difference between measured ions and unmeasured ions.
In basic terms, the anion gap examines the positive-charge and negatively charged components found in usual blood chemistry. Because not every ion is directly measured, the gap can reveal hidden acids or other substances that may be affecting the body’s acid-base status. This makes it especially useful in metabolic acidosis workups.
The standard formula for the anion gap is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some clinicians include potassium in the calculation, but the most widely used version leaves it out. The result is usually expressed in mEq/L, and interpretation depends on the lab’s normal range or the expected range used by the clinician.
For what reason Fix the Anion Gap for Albumin?
Albumin is one of the key negative-charge proteins in blood, so it has a major effect on the calculated anion gap. When albumin is low, the measured gap can look falsely normal or low even when a real acid-base problem is present. This is why hypoalbuminemia matters so much during acid-base interpretation.
Revising the gap for albumin improves accuracy because it accounts for the missing negative charge contributed by low serum albumin. In other words, the corrected anion gap gives a truer picture of the body’s acid load. This is especially important in patients with illness, inflammation, malnutrition, liver disease, or other conditions that decrease albumin.
A standard albumin correction factor is used to estimate how much the gap should rise when albumin is below normal. The goal is to make the adjusted result more reliable for clinical decision-making. This is why an anion gap calculator often includes albumin as an input field.
Revised Anion Gap Formula
The usual anion gap formula reads:
Anion gap = Sodium − (Chloride + Bicarbonate)
To calculate the albumin-corrected anion gap, add an adjustment for decreased albumin. A typical albumin correction is written as:
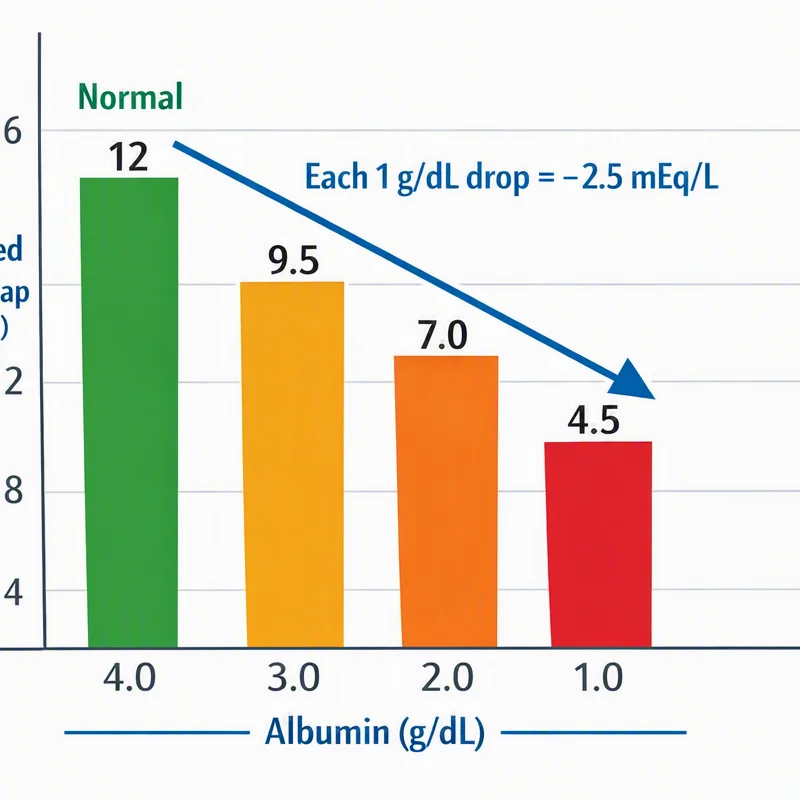
Corrected anion gap = Measured anion gap + 2.5 × (4.0 − albumin in g/dL)
This formula sets 4.0 g/dL as a normal normal albumin value and includes 2.5 mEq/L for every 1 g/dL drop in albumin below 4.0. The exact factor can change somewhat by source, but this version is commonly used in practice. Always interpret the result using your lab’s normal range and the clinical context.
If potassium is added in a local protocol, the equation is changed to:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
However, most calculators and clinical references depend on the sodium-based formula. The corrected value is still reported in mEq/L, and the purpose is to better identify a hidden high anion gap state when albumin is low.
Step by Step: How to Calculate Corrected Anion Gap
To calculate corrected anion gap yourself, begin with the basic test data from the electrolyte panel. Required are serum sodium, serum chloride, serum bicarbonate, and albumin level. These are common laboratory values available on routine blood tests.
Follow this step-by-step formula:
- Step 1: Find the raw anion gap using sodium − (chloride + bicarbonate). Step 2: Check the albumin result with the normal value, usually 4.0 g/dL. Step 3: Calculate the albumin deficit by the albumin correction factor, usually 2.5. Step 4: Include that number to the raw anion gap. Step 5: Assess the corrected result with the expected range.
Example structure:
Raw anion gap = 140 − (104 + 24) = 12 mEq/L
Albumin correction = 2.5 × (4.0 − 2.0) = 5 mEq/L
Corrected anion gap = 12 + 5 = 17 mEq/L
This simple clinical calculation can change the interpretation significantly. A raw value that looks normal may become elevated once albumin is accounted for.
How an Anion Gap Calculator Functions
An anion gap calculator is an internet calculator or healthcare calculator that automates the math for you. It usually provides input fields for sodium, chloride, bicarbonate, and albumin. Some versions also accept potassium, although it is not always necessary.
The calculator calculates the lab values, applies the anion gap correction, and displays a corrected result. This makes it anion gap clinical significance more efficient to evaluate blood chemistry in clinical settings where a quick result analysis is helpful. It also reduces the chance of arithmetic mistakes during busy workflows.
Most calculators display both the raw gap and the albumin-corrected anion gap. That dual output helps clinicians review the unadjusted and adjusted numbers side by side. For users learning the concept, the calculator can also work as an interpretation guide by showing whether the result falls into a normal or elevated range.
Understanding a High or Normal Corrected Anion Gap
A high anion gap usually points to the presence of excess unmeasured acids. This is a key clue in metabolic acidosis evaluation. Common causes include lactic acidosis, ketone-driven acidosis, kidney failure, and toxic exposures.
If the corrected value is elevated, the clinician should evaluate whether a hidden acid load is present even if the raw gap looked normal. This is why the corrected number is such an valuable diagnostic sign. Low albumin can mask the severity of the acid-base problem, and albumin correction helps unmask it.
A normal corrected anion gap after correction may suggest that the raw elevation was mostly due to low albumin. That does not rule out disease, but it modifies the interpretation. In contrast, a persistently high corrected result favors a true acid excess and may guide the next steps in the evaluation of metabolic acidosis.
Helpful interpretation points:
- High corrected gap: suspect hidden acids or excess unmeasured ions. Corrected gap in the normal range: the apparent elevation may be explained by hypoalbuminemia. Low albumin can make a dangerous process look less abnormal than it really is.
Typical Problems in Calculating the Corrected Anion Gap
A frequent mistake is a measurement conversion problem. Albumin may be reported in g/dL or g/L depending on the lab, and the formula only works correctly with the intended unit. Using the wrong unit can distort the result and produce a misleading number.
Another issue is using the wrong reference interval. Different laboratories may list slightly different normal intervals for anion gap, so the same number can be interpreted differently depending on the lab’s standards. Always compare the result with the local expected range.
Some clinicians also forget to consider whether potassium is included. If a formula includes potassium in one setting but not another, the values will not match. That mismatch is a frequent calculation error in hand calculations and in copied notes.
Additional mistakes include:
- Calculating with the raw gap without albumin adjustment when albumin is clearly low. Using bicarbonate instead of total CO2 without understanding the lab report. Assuming every calculator uses the same correction factor. Neglecting the clinical context of the blood chemistry.
Careful review of the inputs prevents misleading conclusions and improves the quality of the final interpretation.
Illustrations of Corrected Anion Gap Calculations
Below is a worked example with typical lab values. Suppose:
- Serum sodium = 138 mEq/L Chloride = 104 mEq/L Bicarbonate = 22 mEq/L Albumin level = 2.4 g/dL
Initially, determine the initial anion gap:
138 − (104 + 22) = 12 mEq/L
Then, calculate the albumin correction:
2.5 × (4.0 − 2.4) = 4.0 mEq/L
Next, apply the correction to the initial anion gap:
Corrected value = 12 MUDPILES high anion gap + 4 = 16 mEq/L
This shows that the adjusted result is higher despite the fact that the raw anion gap was within many labs’ normal range. Low albumin was masking part of the abnormality.
One more worked example:
- Sodium = 142 mEq/L Serum chloride = 100 mEq/L Bicarbonate = 26 mEq/L Albumin level = 4.2 g/dL
Initial anion gap = 142 − (100 + 26) = 16 mEq/L. As albumin is not low, minimal or no correction is needed. The corrected value remains basically the same, and the elevated gap is more apt to reflect a real increase in unmeasured acids.
When You Should Use a Corrected Anion Gap in Clinical Practice
A corrected gap is most valuable when the patient has hypoalbuminemia and an acid-base disorder is being evaluated. It is most useful in critical care, where fluid shifts, inflammation, malnutrition, and organ dysfunction often lower albumin. In those cases, the raw result can be misleading.
It also matters in kidney disease, where acid retention can alter the electrolyte pattern and complicate interpretation. A corrected value can improve the diagnostic picture and help clinicians tell apart between different causes of acidosis.
Another important use is toxic ingestion evaluation. If a patient has unexplained acidosis, an elevated corrected gap may support the presence of hidden acids or toxic compounds. That can affect urgent management decisions.
In clinical use, rely on the corrected value if:
- Albumin falls below the normal range. Metabolic acidosis is suspected. The uncorrected anion gap appears unexpectedly normal or borderline. Clinical findings do not match the measured electrolyte pattern.
When applied like this, the corrected value becomes a practical clinical guide rather than just another number.
FAQ About Anion Gap Calculation
How do you calculate corrected anion gap from lab values?
First determine the original anion gap using sodium − (chloride + bicarbonate). Next correct for albumin using an albumin correction factor, usually 2.5 mEq/L for each 1 g/dL albumin below 4.0. This results in the corrected anion gap, which gives a more accurate clinical calculation when albumin is low.
Why does low albumin change the anion gap?
Albumin is a key negatively charged protein in blood, so reduced albumin levels lowers the number of unaccounted-for negative charges. It can make the calculated anion gap look lower than it really is. Adjusting for albumin helps bring back the expected range and improves acid-base interpretation.
What is the normal corrected anion gap range?
The standard albumin-corrected anion gap range is determined by the laboratory’s reference range, but many clinicians consider it to fall within the expected anion gap range after albumin correction. Because methods vary, always assess the result using the lab’s benchmark range and the patient’s overall clinical context.
Should potassium be included in the anion gap calculation?
Typically, potassium is not part of the usual formula employed by most anion gap calculator tools. A few formulas do include potassium, but that is not as common. If potassium is included, the result will vary, so the method must be in line with the reference or calculator you are using.
When should a corrected anion gap be used rather than the raw anion gap?
Use adjusted anion gap whenever albumin is decreased and you are reviewing an acid-base disorder, especially metabolic acidosis. The corrected value is more accurate in hypoalbuminemia because it reflects hidden changes in unmeasured ions. It is especially helpful useful in critical care, kidney disease, and toxic ingestion workups.