An anion gap calculator is a practical tool for evaluating acid-base balance and refining the differential diagnosis of metabolic acidosis. It assists clinicians and learners transform a basic set of electrolytes into a better diagnostic approach by showing whether unmeasured acids may be present. In the right context, the anion gap is more than a number; it is a guide to next steps in metabolic acidosis evaluation, especially when paired with blood gas analysis and the rest of the electrolyte panel.
The value is obtained from routine serum chemistry results, most often sodium, chloride, and bicarbonate, with potassium sometimes included. Because the result reflects the balance between measured cations and anions, it provides a quick window into possible electrolyte abnormalities, unmeasured anions, and acid retention. The key is not just calculating it, but interpreting it in clinical context.
What is the anion gap?
The anion gap is a calculated value that estimates the difference between measured positive and negative ions in the blood. Put simply, it represents the gap between the major measured cation, sodium, and the major measured anions, especially chloride and bicarbonate. This gap is present because the body contains many unmeasured anions and cations that are not directly listed in routine lab results.
In acid-base physiology, the buffer system helps keep pH within a narrow range. When acids build up, their anions may not be immediately captured on standard labs. The anion gap provides indirect evidence of that accumulation. For this reason, the anion gap is key to interpreting acid-base disorders, particularly metabolic acidosis.
Most anion gap calculation methods rely on a basic formula based on measured electrolytes. The result is not a diagnosis by itself, but it can signal when additional evaluation is needed. That is why an anion gap calculator is helpful in everyday practice: it converts raw lab values into a decision point.
How might the anion gap aid diagnose acid-base disorders?
The anion gap assists distinguish between major categories of metabolic acidosis. A high anion gap indicates that acids are building up in the body, often because of lactate elevation, ketone production, toxin exposure, or reduced elimination. A normal anion gap implies a different pattern, often one in which bicarbonate is being lost and replaced by chloride, producing hyperchloremic acidosis.
This distinction is important because acid-base disorders are not all addressed the same way. A high gap guides you toward causes such as lactic acidosis, ketoacidosis, or renal impairment. A normal gap often suggests gastrointestinal losses or tubular defects. The value therefore acts as a branching point in the diagnostic workflow.
In practice, a clinician assesses the anion gap alongside the blood gas, pH, and bicarbonate level. If bicarbonate is low and the anion gap is high, the pattern supports high anion gap metabolic acidosis. If bicarbonate is low but the anion gap is normal, the pattern supports normal anion gap metabolic acidosis. That first branch guides what to test next.
How do you determine the anion gap?
The usual anion gap formula is:
Anion gap = sodium - (chloride + bicarbonate)
A few clinicians use potassium, but many do not because it has a small effect in most settings. A common alternative is:
Anion gap = (sodium + potassium) - (chloride + bicarbonate)
The calculator usually draws from values on a basic metabolic panel, which is part of a routine electrolyte panel. Since the result is based on the exact numbers entered, even small shifts in sodium, chloride, or bicarbonate can alter the interpretation.
For example, if sodium is 140, chloride is 102, and bicarbonate is 24, the anion gap is 14. This may fall within or slightly above the local reference interval, depending on the laboratory. The point is that the number must be interpreted against the lab’s method and context, not as a universal fixed value.
What is a normal anion gap range?
The normal range is most accurately interpreted as a reference range, rather than a fixed rule. Various labs use different instruments and methods, so the expected value can differ because of lab variation. In addition, the measured range may change depending on whether potassium is included in the calculation.
Albumin is among the most significant factors affecting the apparent normal range. Because albumin carries negative charge, lower albumin can reduce the measured anion gap even when clinically important acids are present. That is why a normal result does not necessarily rule out acid accumulation, especially in patients with hypoalbuminemia.
A thoughtful clinician uses the reported range as a starting point and then considers whether a corrected anion gap is needed. This is especially important when reviewing possible metabolic acidosis in hospitalized patients, where albumin may be reduced and the measured gap can fail to reflect the true burden of acids.
What causes a high anion gap?
A high anion gap metabolic acidosis usually means that acids with unmeasured anions have accumulated. Frequent causes include lactic acidosis, ketoacidosis, renal failure, and toxins. These conditions raise the amount of acids in circulation or reduce the body’s ability to clear them.
In lactic acidosis, lactate increases when tissues are underperfused, hypoxic, or metabolically stressed. In ketoacidosis, ketones build up when insulin is deficient or carbohydrate use is impaired. In renal failure, acids are retained because kidney excretion is reduced. With certain toxins, the issue may be direct acid generation, toxic metabolites, or altered metabolism.
When the anion gap is high, the next step is not merely naming the pattern. It is determining the source. That may require checking lactate, measuring ketones, examining the medication and exposure history, and assessing kidney function. The calculator helps you recognize the pattern; the diagnostic workup clarifies it.
What explains a normal anion gap metabolic acidosis?
Normal anion gap metabolic acidosis is often called hyperchloremic acidosis because chloride rises as bicarbonate falls, keeping the calculated gap near usual. A classic cause is diarrhea, where the body loses bicarbonate through the gastrointestinal tract. Another key cause is RTA, where the kidneys fail to acidify urine or conserve bicarbonate appropriately.
In these circumstances, the issue is usually reduced bicarbonate rather than accumulation of unmeasured acids. The fall in bicarbonate is offset by a rise in chloride, so the gap may look normal even though the patient is acidemic. This is a common reason why the anion gap should be interpreted with the ABG and the rest of the chemistry profile.
Recognizing this pattern helps separate gastrointestinal losses from renal acid-handling disorders. That distinction has major clinical implications because treatment differs depending on whether the source is the bowel, the kidney, or both.
How do albumin and the corrected anion gap change interpretation?
Albumin has a significant effect on the anion gap because it contributes a large share of the body’s negative charge. In hypoalbuminemia, the measured gap can appear artificially low even when there are excess acids present. This is why albumin correction is important in acid-base interpretation.
The idea behind the corrected anion gap is straightforward: if albumin is low, the expected gap should be adjusted upward to account for the missing negative charge. The exact anion gap correction formula may vary by source, but the goal is the same—avoid underestimating acid burden. This is especially important in critically ill patients, where low albumin can mask clinically significant high-gap disease.
Because albumin reflects protein charge, its reduction changes the balance of measured and unmeasured ions. A normal measured gap in a patient with severe hypoalbuminemia should prompt close attention. In that setting, the corrected value may reveal unrecognized metabolic acidosis that would otherwise be missed.
What is the delta gap and why does it matter?
The delta gap, also called delta-delta, evaluates the rise in the anion gap to the fall in bicarbonate. It helps determine whether the patient has only one acid-base problem or a mixed acid-base disorder. This matters because a high anion gap alone does not guarantee a straightforward diagnosis.
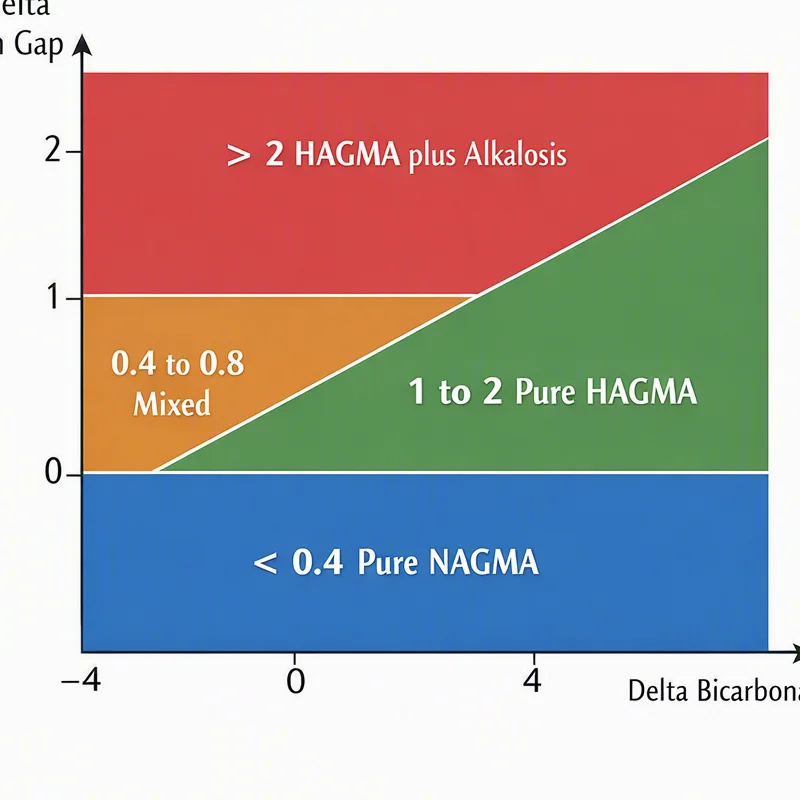
Conceptually, the delta gap asks whether the increase in unmeasured acids matches the drop in bicarbonate. If the rise in gap is higher than the fall in bicarbonate, there may be a concurrent metabolic alkalosis or a preexisting low bicarbonate state. If bicarbonate falls more than expected, there may be an additional normal-gap acidosis on top of the high-gap process.
This is why delta-delta analysis is useful in patients with complex illness. For example, someone with ketoacidosis may also have vomiting, renal dysfunction, or diarrhea. The delta gap helps expose that layering so the final diagnosis reflects the overall acid-base picture rather than just the first abnormality seen.
How should an anion gap calculator be used in clinical practice?
An anion gap calculator functions best as part of a structured diagnostic workflow, not as a single solution. First, check the basic laboratory values and assess whether the patient truly has acidemia or bicarbonate loss. Then interpret the gap in clinical context, including symptoms, hemodynamics, medication use, and possible exposures.
A practical sequence is:
- Review the serum chemistry or basic metabolic panel. Determine the anion gap from sodium, chloride, and bicarbonate. Assess whether albumin is low and whether a corrected anion gap is needed. Use the blood gas analysis or arterial blood gas to confirm the acid-base state. Evaluate lactate, ketones, kidney function, and exposure history. Assess for a mixed acid-base disorder with delta-delta if the pattern seems inconsistent.
This approach is especially helpful in metabolic acidosis evaluation because the anion gap helps identify the cause while the rest of the data show whether the pattern is https://anion-gap-tool752.lowescouponn.com/can-pregnancy-affect-the-anion-gap pure or mixed. A calculator saves time, but interpretation still depends on clinical reasoning.
Common pitfalls when interpreting the anion gap
One major pitfall is measurement error. If the electrolyte values are inaccurate, the calculated gap will be inaccurate too. Even small analytic differences in chloride or bicarbonate can change the impression. Another pitfall is albumin bias, where low albumin makes the gap appear normal despite significant acid accumulation.
It is also easy to forget about unmeasured ions. The gap is influenced by substances not directly reported on a standard panel, so unusual exposures, paraproteins, or unusual electrolyte shifts can alter the result. Likewise, mixed disorders can hide the expected pattern. A patient may have high-gap acidosis plus metabolic alkalosis, or normal-gap acidosis plus respiratory compensation, making the numbers harder to read.
The most prudent way of thinking is to view the anion gap as one part of the whole clinical picture. If the result is not consistent with the patient, re-evaluate the data, redo labs if needed, and weave in the history rather than making the number to explain the whole story.
When should you order additional tests?
Additional testing is appropriate when the anion gap suggests a serious cause or when the clinical picture remains unclear. If the gap is high, check lactate to look for lactic acidosis, and measure ketones when ketoacidosis is a concern. If toxic exposure is a possibility, evaluate the osmolar gap as part of the evaluation for toxic ingestion.
An arterial blood gas is helpful when you need accurate pH, respiratory compensation, and support of the acid-base disorder. This is especially useful when the chemistry panel and symptoms do not line up neatly. In patients with possible renal impairment, the blood gas and chemistry alongside each other can show whether the acidosis is metabolic, respiratory, or mixed.
Additional evaluation should be driven by the suspected cause. The point is not to order every test for every patient, but to use the anion gap to narrow the field and then choose targeted studies that explain the abnormality.
Frequently asked questions about the anion gap
What does a high anion gap mean?
A high anion gap usually suggests there are extra acids in the blood that are not directly measured on the standard chemistry panel. Common causes include lactic acidosis, ketoacidosis, renal failure, and certain toxins. In practice, it often points to high anion gap metabolic acidosis and should warrant further evaluation.
How do you calculate the anion gap from lab values?
Calculate with the anion gap formula: sodium minus the sum of chloride and bicarbonate. Some versions include potassium, but many clinicians omit it. The calculation is usually based on values from a basic metabolic panel or other electrolyte panel.
Why might low albumin affect the anion gap?
Albumin is a negatively charged protein, so when it is low, the calculated anion gap can be lower than expected. This is why hypoalbuminemia can mask a true gap elevation. Applying albumin correction or a corrected anion gap helps account for that protein charge effect.
What is the delta gap in acid-base diagnosis?
The delta gap, or delta-delta, contrasts the change in anion gap with the change in bicarbonate. It is used to spot a mixed acid-base disorder when one problem may be concealing another. It is especially useful when the diagnosis seems complicated than a single metabolic process.
Can a normal anion gap still indicate metabolic acidosis?
Indeed. A normal anion gap can still occur in normal anion gap metabolic acidosis, often due to diarrhea or renal tubular acidosis. In those cases, the patient loses bicarbonate and accumulates chloride, producing hyperchloremic acidosis without a large gap increase. That is why the anion gap calculator should always be interpreted with the full clinical picture.