What the anion gap measures in alkalemia
The anion gap is a useful way to evaluate acid-base balance by reviewing measured electrolytes in a standard serum chemistry panel. An Anion Gap Calculator aids estimate whether there are unmeasured acids in the blood, which can suggest a hidden metabolic disorder even when the pH shows alkalemia. In practical terms, the anion gap is a diagnostic tool that supports clinicians spot acid accumulation or an anion deficit that may not be obvious from the pH alone.
Alkalemia means the blood is more alkaline than normal, but that does not guarantee the absence of an underlying acid problem. A patient can have alkalosis and still have a concurrent elevated anion gap from another process. This is why clinical interpretation matters: the number from the calculator is only one part of the overall picture. The goal is to interpret results in the clinical context, not treat the anion gap as a standalone answer.
In alkalemia, the anion gap can help reveal whether a masked acid load is present. For example, a patient with metabolic alkalosis from vomiting may also have lactic acid production from poor perfusion, leading to a mixed pattern. Similarly, respiratory alkalosis can coexist with a high anion gap process, especially if there is a compensatory response or another mixed disorder. The calculator is most helpful when it is used to move past the pH and identify the complete acid-base story.
Anion gap calculation and required inputs
An anion gap calculator typically uses the main laboratory values from a standard metabolic panel: sodium, chloride, and bicarbonate. Some equations also use potassium, though many common clinical approaches omit it because potassium is usually a minor contributor to the result. The classic corrected formula is:
Anion gap = sodium − (chloride + bicarbonate)
If potassium is included, the formula becomes:

Anion gap = sodium + potassium − (chloride + bicarbonate)
The exact equation used by a calculator can change the final number, which is why it is important to know the method behind the result. Different laboratories may use slightly different analytic methods, and the reference range may vary accordingly. That makes the calculator a practical first step, but not a substitute for reviewing the actual serum chemistry report.
In a patient with alkalemia, these inputs help reveal whether the apparent alkalosis is isolated or whether the chemistry suggests a hidden acid-base problem. For example, a low bicarbonate might be unexpected in alkalosis and could signal a mixed disorder. A higher chloride can reduce the gap, while a lower chloride may increase it. Because the calculation depends on multiple electrolytes, small shifts in any one of them can affect the interpretation.
In what way alkalemia can alter the reading
Alkalemia can render interpretation challenging because a high pH might draw focus away from the underlying metabolic pattern. A patient with metabolic alkalosis may also have an elevated anion gap from another cause, which produces a mixed acid-base disorder. In other cases, respiratory alkalosis from hyperventilation reduces carbon dioxide and can coexist with an acid-base abnormality that is not obvious without an arterial blood gas.
For this reason an anion gap result should be reviewed alongside blood gas data. The arterial blood gas provides pH, carbon dioxide, and bicarbonate estimates that help reveal whether the primary problem is respiratory or metabolic. Blood gas analysis may also reveal respiratory compensation, which helps distinguish a simple disorder from a more complex mixed picture. Without this context, alkalemia can lead to premature conclusions.
A common mistake is assuming that alkalemia excludes acid production. It does not. A patient can have alkalemia from vomiting, diuretic use, or hyperventilation while also having a concurrent high anion gap metabolic process. In those situations, the calculator is not just a number generator; it is an approach to uncover a hidden mixed disorder and improve diagnostic accuracy.
Corrected for albumin anion gap
Albumin is a important unmeasured anion in blood, so variations in serum albumin can substantially affect the measured gap. If albumin is low, the apparent anion gap may seem normal even when an elevated acid load is present. That is why many clinicians use an albumin-corrected anion gap to refine interpretation. This corrected formula is especially important when looking for occult acid-base disorders in patients with illness, malnutrition, inflammation, or fluid shifts.
Hypoalbuminemia decreases the baseline gap, which can mask a significant problem. In that setting, the uncorrected number may land within the reference range and look reassuring when it is not. Correcting for albumin improves diagnostic accuracy and helps identify an otherwise subtle elevated anion gap. This is especially useful when the clinical picture suggests a metabolic issue but the raw chemistry panel seems borderline.
Many calculators now include albumin correction because it enhances bedside interpretation. If a patient has alkalemia and a low albumin, the corrected result may reveal a concealed acid-base disorder. The key point is that the anion gap calculator should be treated as a diagnostic aid, not an isolated value. When albumin is low, the corrected result often more accurately reflects the true state of acid-base balance.
Stepwise reading illustrations
Example case: A patient presents with nausea and vomiting, weakness, and blood alkalosis on blood gas testing. The lab panel shows sodium 140, chloride 92, and bicarbonate 34. The uncorrected anion gap is 140 − (92 + 34) = 14, which may be around the local reference range. Initially, that may seem consistent with isolated metabolic alkalosis. But interpretation does not stop there.
If albumin is low, the albumin-corrected anion gap may be more elevated than expected. If lactate is elevated, then a hidden metabolic acidosis could be present as well. In this scenario, the vomiting explains the alkalemia, while the lactate suggests another process that increases acid burden. This is a typical example of why the calculator should be used as part of a larger acid-base assessment.
Delta gap analysis can add another layer of insight. The delta gap compares the change in anion gap with the change in bicarbonate to help identify a mixed disorder. If the anion gap is elevated but bicarbonate is not as low as expected, there may be concurrent metabolic alkalosis. If bicarbonate is lower than the gap suggests, an additional metabolic acidosis may be present. This approach is especially helpful when alkalemia and a high anion gap appear to conflict.
Another case example involves a patient with elevated lactate and hyperventilation. The arterial blood gas shows alkalemia, but the chemistry panel suggests a hidden high anion gap process. This pattern may reflect early sepsis, tissue hypoperfusion, or another cause of lactate production. The final interpretation depends on whether the alkalemia is driven by respiratory alkalosis, metabolic alkalosis, or a compensatory response layered over another problem.
Common causes of an elevated anion gap with alkalemia
A raised gap with alkalemia usually suggests multiple processes are occurring. These causes include lactic acid buildup, ketone-related acidosis, kidney failure, and toxic alcohol ingestion. These conditions increase unmeasured acids, but the pH may still be alkaline if another process is driving the acid-base picture.
Lactate accumulation can coexist with alkalemia when there is hyperventilation or vomiting. As an example, a patient with severe pain, infection, or poor perfusion may generate lactate while also breathing rapidly, producing respiratory alkalosis. The final pH can remain high even though the chemistry indicates acid accumulation.
Ketone-related acidosis is another significant cause. Although it classically causes acidemia, a patient may have vomiting or volume depletion that pushes the pH toward alkalemia. In addition, treatment before the blood draw can partially shift the pattern. Kidney failure can also produce an elevated anion gap because acids are not cleared effectively, but concurrent vomiting or diuretics may obscure the acidosis.
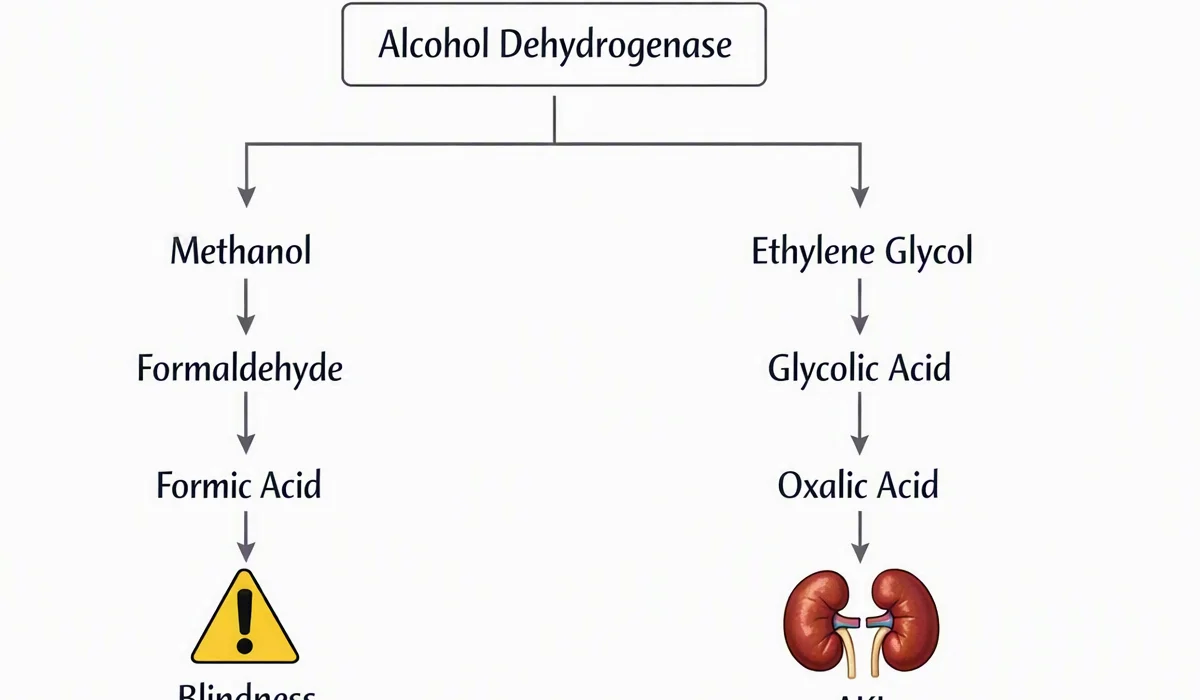
Toxic alcohols deserve special attention because they can produce a dangerous high anion gap metabolic acidosis that may be masked early by hyperventilation or mixed physiology. A calculator can help raise suspicion, but the result must always be interpreted with the clinical history, symptoms, and blood gas pattern.
When a standard anion gap may be misleading
A regular anion gap does not automatically mean there is no clinically important acid-base disorder. During alkalemia, a normal result can be misleading when there is a hidden acid load balanced by another process. For example, vomiting may raise bicarbonate, while a simultaneous acid-producing condition pushes the gap upward just enough to appear normal.
A chloride change can also complicate interpretation. If chloride falls because of volume depletion or gastric loss, the anion gap may look unchanged even though the underlying physiology is changing. This is why the values must be viewed as an overall pattern rather than a single number. The presence of emesis or diuretic therapy can strongly influence chloride and bicarbonate, creating a picture that appears straightforward but is actually mixed.
Diuretic use may increase bicarbonate and lower chloride, producing metabolic alkalosis. However, if another process such as lactate production or ketosis is occurring, the gap may be underestimated or appear deceptively normal. In these cases, the calculator helps uncover whether a second metabolic process is being https://jsbin.com/siyoneheqo masked by the alkalosis.
Restrictions, drawbacks, and the clinical picture
Even a carefully built anion gap calculator has constraints. Laboratory variation is a fact, and different analyzers may generate slightly different results. Small analytic differences can matter when the gap is borderline. That is why trends, repeat measurements, and the surrounding clinical context are often more revealing than a single value.
Ionized calcium can also affect interpretation indirectly because shifts in protein binding and charge balance may alter overall electrolyte behavior. While it is not part of the standard formula, it can matter in serious illness. Likewise, blood gas analysis may disagree somewhat with chemistry bicarbonate because the values come from different measurement systems. Reconciling these results requires careful review rather than automatic acceptance of one source over another.
The best practice is to interpret together the gap with the patient’s complaints, medication history, fluid status, and acid-base data. This is the essence of clinical correlation. If alkalemia is present, ask whether there is a primary metabolic or respiratory process, whether a compensatory response is expected, and whether a second disorder may be hidden. The calculator strengthens interpretation, but only when it is used as part of a broader diagnostic strategy.
Frequently asked questions about anion gap calculator use
What does an anion gap calculator show in alkalemia?
An anion gap calculator shows whether there is an unmeasured acid burden or other electrolyte pattern that may be hidden despite a high pH. In alkalemia, it helps identify a possible mixed acid-base disorder rather than assuming the alkalosis is isolated. It is most useful when combined with blood gas analysis and clinical correlation.
Can alkalemia hide a high anion gap metabolic acidosis?
Yes. Alkalemia can coexist with a high anion gap metabolic acidosis when another process such as vomiting or hyperventilation is driving the pH upward. This is one of the most important reasons to use anion gap calculator carefully. The pH alone can be misleading if there is a mixed disorder.
Should albumin always be corrected when determining the anion gap?
It is not necessarily mandatory, but it is often helpful, especially when albumin is decreased or the clinical picture is complex. The albumin-corrected anion gap enhances interpretation when hypoalbuminemia could otherwise just mask a true elevation. Many clinicians tend to correct when looking for underlying metabolic disorders.
What is the normal anion gap range used by most labs?
The reference range differs by laboratory method and whether potassium is included in the formula. Because of this, it is crucial to use the range listed by the lab running the test. A value that is within range in one setting may be somewhat abnormal in another.
What conditions can cause an elevated anion gap with alkalosis?
Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. These can coexist with metabolic alkalosis or respiratory alkalosis, creating a mixed picture that produces alkalemia overall. Vomiting and diuretics can also add to the alkalotic component while another process elevates the gap.