The typical anion gap for infants is generally close to though not always exactly the same as the adult range. In many pediatric interpretation settings, the expected normal range is roughly 8 to 16 mEq/L, though the specific pediatric reference range depends on the laboratory, the child’s age, and whether the result is corrected for albumin. As a result, a result should carefully be read in the clinical context of the infant’s overall health, symptoms, and other blood chemistry panel findings.
The anion gap is a useful calculated measurement that helps assess electrolyte balance and acid-base status. It is frequently used as a diagnostic clue when searching for a possible metabolic disturbance. An Anion Gap Calculator can simplify the calculation, but the real value comes from understanding what the number means in an infant, especially when the serum sodium, serum chloride, and serum bicarbonate levels are varying during illness or recovery.
What Is the Anion Gap?
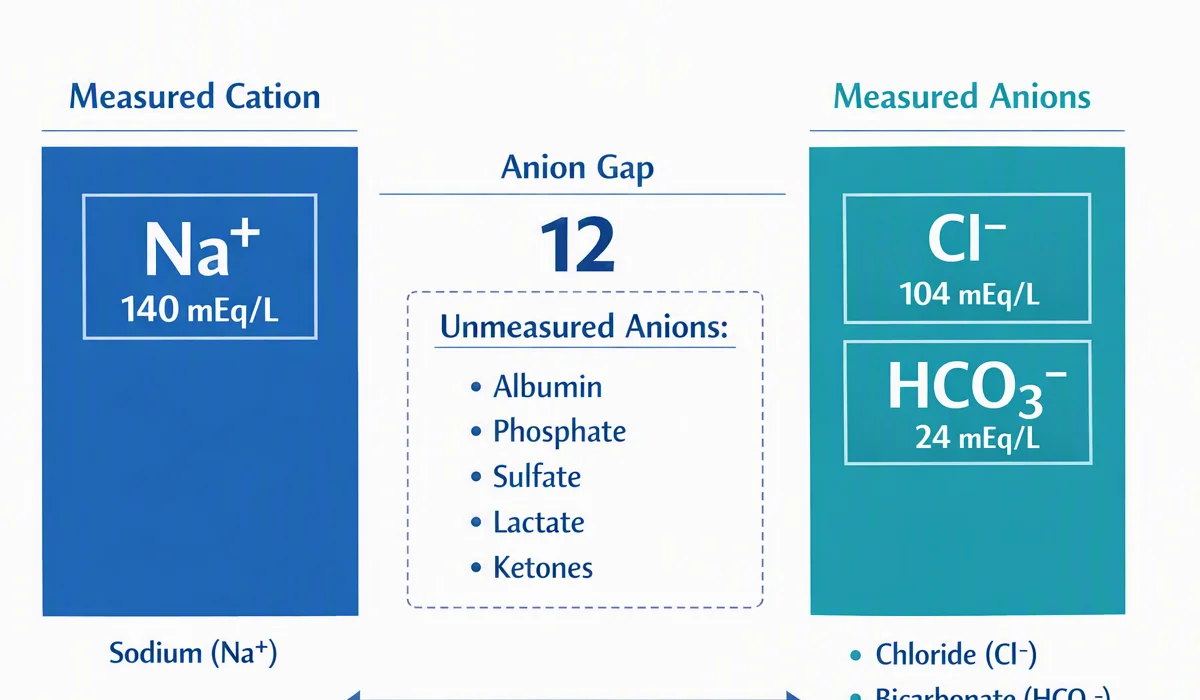
The anion gap is a lab value calculated from common electrolytes measured in a blood sample. It estimates the difference between the major positively charged ions and the major negatively charged ions in the blood. In practical terms, it helps clinicians think about whether there are unmeasured acids or other substances influencing the body’s buffering system.
The most common version of the calculation uses sodium, chloride, and bicarbonate. Because these values are part of a routine serum chemistry panel, the anion gap is not directly measured. Instead, it is a calculated measurement based on other lab results. That is why the anion gap formula is so important for accurate interpretation.
In simple terms, the anion gap helps indicate whether the difference between the measured cations and anions is within the expected range. When the result is abnormal, it may point to an underlying cause such as acid accumulation, albumin changes, or a testing issue. However, one value alone does not diagnose a condition. It is only one piece of the larger picture of acid-base status and overall health.
Expected Anion Gap Range for Infants
The normal anion gap for infants is commonly viewed close to the pediatric and adult reference interval reported by numerous laboratories. A common expected range is about 8 to 16 mEq/L, though different laboratories may report slightly different limits. Because newborn physiology is still adjusting after birth, the exact reference interval can vary by age, feeding status, and lab method.
For recently born infants, values may shift somewhat during the first days of life. This is why the result should be interpreted using an infant-specific pediatric reference range rather than assuming a single universal number applies to every infant. The lab’s own report is often the best starting point for interpretation.
Another important detail is that the anion gap can be influenced by the serum bicarbonate level. When bicarbonate is lower, the gap may rise if the body is responding to an acid load. When bicarbonate is higher or chloride changes in the opposite direction, the gap may appear lower. That means the same number can have different meanings depending on the full chemistry pattern.
For this reason, a normal result does not always rule out illness, and an abnormal result does not always mean severe disease. The number must be viewed alongside the infant’s symptoms, hydration status, feeding history, and other blood chemistry panel results.
How an Anion Gap Calculator Operates
An Anion Gap Calculator employs a simple calculation formula based on measured lab values. The most common formula is:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
This equation starts with the serum sodium value and removes the sum of serum chloride and serum bicarbonate. The result is the calculated measurement called the anion gap. Because the calculation is calculated from routine lab data, it is often available quickly once the chemistry panel is complete.
Some calculators may also offer a correction for albumin, since low albumin can lower the measured gap. That makes the tool especially useful in pediatric interpretation, where changes in protein levels and fluid balance can affect the result. Even so, the calculator is only as accurate as the numbers entered, and it cannot replace medical judgment.
When using an Anion Gap Calculator, it helps to remember these factors:
- The calculation depends on accurate serum sodium, serum chloride, and serum bicarbonate values. The result is a calculated measurement, not a directly measured laboratory value. Age, albumin, and the clinical context affect interpretation. Small differences can occur because of measurement variability between laboratories.
So, while the calculator can quickly show the number, the meaning of that number depends on whether the infant’s acid-base status and overall laboratory pattern align with a certain condition.
How Infant Ranges Differ From Adults
Infant results are not always interpreted exactly the same way as adult results because of age-dependent reference ranges. Babies are still developing kidney function, fluid regulation, and metabolic control, and these factors can affect the chemistry panel. In newborns, this is especially true because the body is shifting from fetal to postnatal life.
Pediatric patients often have varied expected laboratory patterns than adults due to growth, feeding changes, and developmental physiology. The kidneys, lungs, and liver all play roles Look at this website in maintaining the body’s electrolyte balance and buffering system, and those systems are still maturing in early life. As a result, the same laboratory value can have a different interpretation in an infant than it would in an older child or adult.
Albumin is also important. Because albumin carries negative charge in the blood, lower levels can decrease the anion gap without necessarily indicating a dangerous condition. This is one reason clinicians may consider adjusted interpretation when hypoalbuminemia is present. The result may look low simply because less albumin is available to participate to the charge balance.
In addition, mild differences in method, specimen handling, or analyzer calibration can lead to measurement variability. That is why a single laboratory value should not be considered in isolation. A careful pediatric interpretation reviews trends, symptoms, and other labs together.
Why a Raised Anion Gap May Point To
A high anion gap may be an important clue to metabolic acidosis. This means the body may have too much acid or a low bicarbonate level available to absorb acid. Among infants, this finding often prompts a closer look at feeding, hydration, perfusion, and overall illness severity.
One possible cause is lactic acidosis. Lactic acid can rise when tissues are not getting enough oxygen or when the body is under significant stress. Another cause is ketosis, which may occur when an infant is not taking in enough calories, is vomiting, or has another condition affecting glucose use. In these situations, the anion gap helps point toward an underlying cause of the metabolic disturbance.
Renal failure is another important cause because the kidneys normally help remove acids from the body. If kidney function is reduced, acids can accumulate and push the gap upward. Other disorders can also contribute, but the main point is that a high number often suggests acid accumulation rather than a simple electrolyte shift.
When the gap is high, clinicians often check the full blood chemistry panel, including bicarbonate, creatinine, glucose, and chloride level. The result is best interpreted as a diagnostic clue, not a final diagnosis. A metabolic acidosis pattern in an infant should always be interpreted with the child’s symptoms and exam findings.
What a Low Anion Gap May Suggest
A low anion gap is not as common than a high one, but it can still be significant. One of the most common explanations is hypoalbuminemia. Since albumin contributes anionic particles, low albumin can lower the gap even when the infant is otherwise clinically stable.
Another possibility is lab error. Because the anion gap is calculated from multiple measurements, a small issue in one component can distort the final value. If the result does not match the infant’s condition, repeat testing or review of specimen handling may be warranted.
Paraproteinemia is a uncommon cause in infants, but it is part of the broader differential for a low result. Another cause is hyperchloremia, in which the chloride level is relatively high compared with sodium and bicarbonate. That shift can reduce the calculated difference and make the gap appear low.
When a low gap is found, clinicians often ask whether the number matches the rest of the lab picture. Is the infant well hydrated? Are other values unremarkable? Is there a known protein abnormality or a reason for low albumin? These questions help determine whether the low value is important or simply a reflection of measurement conditions.
When to Consult a Pediatric Clinician
If an infant has unusual blood chemistry panel results, a pediatrician or other pediatric clinician should evaluate them. This is especially important when the anion gap is outside the expected range or when the infant has alarming clinical symptoms such as poor feeding, vomiting, lethargy, rapid breathing, dehydration, or changes in alertness.
A medical professional can place the result into the correct clinical context, check whether the values fit the baby’s age, and decide whether further testing is needed. A single abnormal result does not always mean something serious, but it should not be ignored if the infant seems sick.
Seek a medical evaluation when the laboratory value is clearly abnormal, when symptoms are present, or when the result does not match the child’s condition. The clinician may review repeat chemistry testing, glucose, blood gas results, kidney markers, and albumin to understand the full picture.
In short, the anion gap is helpful because it can highlight a hidden problem, but it is not a stand-alone diagnosis. The combination of the laboratory value, age-specific expectations, and the infant’s overall condition is what shapes care.
Frequently Asked Questions
What is considered a normal anion gap for infants?
A normal anion gap for infants is often around 8 to 16 mEq/L, but the exact normal range depends on the laboratory and the infant’s age. The result should be interpreted using the lab’s pediatric reference range and the child’s overall health picture.
Is the anion gap different in newborns compared with older infants?
Yes, it can be. Newborns may have slightly different laboratory patterns during the first days of life, so the reference range can differ from that used for older infants. Age-specific reference ranges are important for correct interpretation.
How do you calculate the anion gap using an Anion Gap Calculator?
An Anion Gap Calculator typically uses the anion gap formula: serum sodium minus the sum of serum chloride and serum bicarbonate. The calculator returns a calculated value that helps assess acid-base status, but the interpretation depends on the full laboratory picture.
Can a regular anion gap still be present with sickness in an infant?
Yes. A normal calculated value does not eliminate illness. An infant can still have signs or an additional issue even if the anion gap is normal. The overall interpretation always depends on the full set of results, not just one individual laboratory value.
When should a high or low anion gap in an infant be checked by a doctor?
A high or reduced anion gap should be checked by a doctor when it is outside the expected range, when the infant has clinical symptoms, or when the value does not align with the rest of the blood test results. A pediatrician can decide whether repeat testing or further medical evaluation is needed.