What Is the Meaning of the Anion Gap?
The anion gap is a calculated value used to help determine the cause of an acid-base imbalance. It compares with the main measured positive ions and negative ions in blood, especially serum sodium, serum chloride, and serum bicarbonate. In basic terms, it suggests the amount of unmeasured anions in the bloodstream.
The classic calculation is rooted in the idea that blood should remain electrically neutral. When bicarbonate declines and chloride does not fully explain the change, the result may be an elevated anion gap. That pattern often indicates a buildup of acids, which is why the anion gap is so useful in the workup of metabolic acidosis.
A high anion gap usually signals an increased acid load in the body. Instead of losing bicarbonate alone, the body may be accumulating lactate, ketones, or toxins. This is why the anion gap is not a diagnosis by itself, but a guide that guides clinical interpretation and differential diagnosis.
How an Anion Gap Calculator Helps Identify Acidosis
An Anion Gap Calculator makes easier anion gap calculation by using the electrolyte panel values already reported on a lab result. By entering the serum electrolytes, clinicians can rapidly identify whether the patient has a normal or elevated anion gap and whether the pattern suggests metabolic acidosis.
This matters because symptoms and vital signs may be unclear. A patient with fatigue, nausea, rapid breathing, or confusion may have an acid-base problem, but the exact cause is not obvious without reviewing labs. The calculator supports faster lab interpretation by linking chemistry values to the most likely underlying process.
For example, a low serum bicarbonate with a high anion gap suggests actual acid buildup rather than a simple chloride shift. That finding prompts evaluation for lactic acidosis, ketoacidosis, renal failure, or toxic alcohols. In short, the calculator helps guide the workup before more advanced testing such as blood gas analysis or toxin screening.
It also helps identify patterns that may be missed if the clinician focuses on one abnormal value alone. Because the anion gap is a calculated number, it serves as a bridge between symptoms, chemistry results, and the broader acid-base disorder.
Common Causes of Elevated Anion Gap Metabolic Acidosis
The leading causes of high anion gap metabolic acidosis are disorders that produce excess acid or decrease acid clearance. The major categories include lactic acidosis, ketoacidosis, renal failure, and ingestion of toxic alcohols. Each condition has a different clinical context, but all can produce a similar laboratory pattern: low serum bicarbonate and an increased anion gap.
Identifying the source of the acid helps focus the diagnosis. Some causes reflect critical illness and tissue oxygen debt, while others point to impaired metabolism or toxin exposure. The pattern can also change over time, which is why the same patient may need repeat labs, arterial blood gas testing, and careful trend review.
Lactate-Related Acidosis
Lactic acidosis occurs when lactate accumulates faster than the body can clear it. This often happens in critical illness when tissues do not receive enough oxygen. Common triggers include hypoperfusion, sepsis, and tissue hypoxia.
anion gap clinical significanceIn sepsis, for example, inflammation and poor circulation can reduce oxygen delivery and shift metabolism toward anaerobic pathways. That leads to lactate accumulation, which adds acid to the bloodstream and raises the anion gap. The patient may appear ill, tachypneic, or hypotensive, and the acid-base problem may worsen rapidly if the underlying cause is not treated.
Lactic acidosis can also occur with shock, major organ dysfunction, or severe respiratory compromise. Because lactate is not always directly reflected in symptoms, the anion gap may be one of the earliest clues that an acid-base problem is present. In that setting, the calculator is useful for recognizing the pattern and prompting urgent evaluation.
Ketoacidosis in Diabetes, Alcohol Use, and Starvation
Ketoacidosis develops when the body produces excess ketones as an alternate fuel source. This happens when insulin is absent or insufficient, carbohydrate intake is very low, or alcohol use disrupts normal metabolism. The three major forms are diabetic ketoacidosis, alcoholic ketoacidosis, and starvation ketoacidosis.
In diabetes-related ketoacidosis, severe insulin deficiency drives fat breakdown and ketone formation. The ketones are acidic and quickly lower serum bicarbonate, producing an elevated anion gap. Patients often have fluid loss, stomach pain, vomiting, rapid breathing, and marked signs of metabolic acidosis.
Alcohol-related ketoacidosis usually follows heavy alcohol use with poor food intake and vomiting. Starvation ketoacidosis can occur after long periods without food or very low caloric intake. While these conditions may be less striking than diabetic ketoacidosis, they still create a medically significant acid-base disturbance. The anion gap calculator helps distinguish them from other causes of acid accumulation, especially when glucose levels are not markedly elevated.
These disorders are especially important because treatment differs from lactic acidosis or toxin ingestion. Recognizing the pattern early can prevent worsening dehydration, electrolyte abnormalities, and organ failure.
Kidney Failure and Uremia
Renal insufficiency is a major cause of high anion gap metabolic acidosis because the kidneys normally excrete acid and regenerate bicarbonate. When kidney function declines, acids accumulate and renal acid retention develops. This leads to uremic buildup, a buildup of retained waste products that contributes to an elevated anion gap.
Both AKI and CKD can produce this pattern. In acute kidney injury, the rise in acid may be sudden, especially if caused by shock, dehydration, medication toxicity, or severe illness. In chronic kidney disease, the process is often slower, but the anion gap may climb as renal clearance worsens.
Uremic acidosis is important because it may coexist with fluid overload, hypertension, anemia, or other signs of organ dysfunction. The lab pattern can overlap with other causes, so clinical context matters. Anion gap calculation, alongside creatinine and blood gas analysis, helps clarify whether kidney dysfunction is the main driver of the acid-base imbalance.
Toxin Exposure and Drug Ingestion
Toxin exposure is a serious cause of elevated anion gap metabolic acidosis. The classic agents are methanol, ethylene glycol, and salicylates. These exposures can create a toxic syndrome with quick worsening, and the anion gap may be one of the initial clues.
Methanol is metabolized into toxic acids that can damage the eyes and central nervous system. Ethylene glycol, often found in antifreeze, can cause profound acidosis and organ injury after ingestion. Salicylates can create a mixed albumin corrected anion gap low albumin acid-base picture, sometimes with respiratory alkalosis plus an elevated anion gap metabolic acidosis.
These cases require prompt identification because treatment may include antidotes, supportive care, and sometimes dialysis. A calculator can flag an elevated gap, but it cannot identify the specific toxin. That is why the lab result must be interpreted with history, exam findings, and targeted testing. When the clinical story suggests ingestion, the elevated anion gap should heighten concern for a potentially critical emergency.
Less Common Causes
Although uncommon, several other disorders can cause high anion gap metabolic acidosis. Rhabdomyolysis may contribute through muscle breakdown and associated metabolic stress, especially in severe illness or trauma. 5-oxoproline accumulation can occur in some medication-related settings, particularly with prolonged acetaminophen use and other risk factors. D-lactic acidosis may appear in patients with altered gut anatomy or abnormal carbohydrate handling.
These causes are often overlooked because they are not as familiar as lactic acidosis or ketoacidosis. Still, they matter in the appropriate clinical context, especially when the usual explanations do not fit. If the anion gap remains elevated but common etiologies are excluded, these less common diagnoses should move higher on the list of possibilities.
How to Interpret the Anion Gap in Clinical Context
The measured anion gap value is only the starting point. Proper interpretation depends on albumin, the overall acid-base status, and whether the patient has more than one disorder at the same time. Because albumin is a anion-rich protein, low albumin can make the measured anion gap appear spuriously normal or only mildly elevated.
That is why clinicians often apply the corrected anion gap. This correction accounts for hypoalbuminemia and can reveal hidden acid accumulation that the uncorrected value underestimates. In patients with severe illness, the corrected value may be much more informative than the raw number alone.
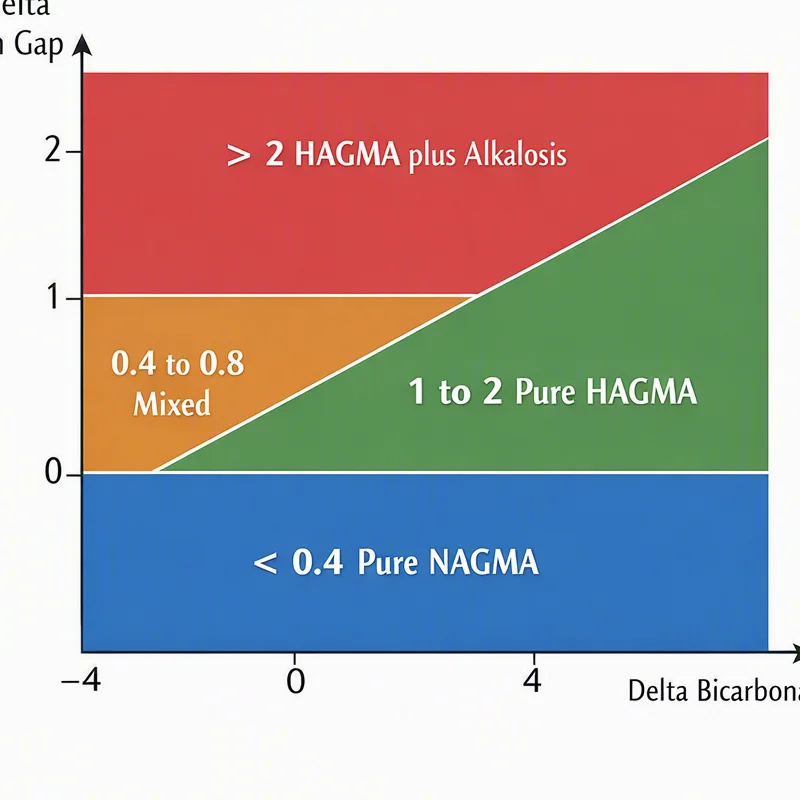
The delta gap is an additional useful tool. It compares the change in the anion gap with the shift in bicarbonate to help detect mixed acid-base disorders. For example, a patient may have elevated anion gap metabolic acidosis plus a separate metabolic alkalosis from vomiting. Without the delta gap, that mixed pattern might be missed.
In practice, the best approach combines the calculator, the electrolyte panel, albumin correction, and blood gas analysis. This gives a more complete picture of the acid-base imbalance and enhances clinical interpretation.
When Severe Anion Gap Metabolic Acidosis Is an Urgent Emergency
Severe anion gap metabolic acidosis turns into an emergency when the patient exhibits signs of physiologic stress or rapid deterioration. Warning features include tachypnea, altered mental status, and shock. These signs suggest that the body is struggling to compensate for the acid load or that a serious underlying cause is present.
An arterial blood gas can help verify the severity of acidosis and evaluate respiratory compensation. If the patient is breathing rapidly, that may represent a compensatory response to lower carbon dioxide levels. However, compensation has limits. Profound acidosis can overwhelm the body, leading to cardiovascular instability, worsening confusion, and organ failure.
Emergency evaluation is especially important when the cause could be sepsis, toxic ingestion, severe ketoacidosis, or kidney failure. These conditions can progress quickly and may require immediate treatment, including fluids, insulin, antidotes, dialysis, or intensive care monitoring. If a patient has concerning symptoms together with an elevated anion gap, prompt assessment should not be delayed.
FAQ: High Anion Gap Acidosis
How should you understand a high anion gap mean?
A high anion gap often suggests there are extra acids or unmeasured anions in the blood. It is a clue that aids in identifying the cause of metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, kidney failure, and toxin exposure. The number itself does not give the diagnosis, but it narrows the differential diagnosis.
Which are the most common causes of high anion gap metabolic acidosis?
The most common causes are lactic acidosis, ketoacidosis including diabetic ketoacidosis, alcoholic ketoacidosis, and starvation ketoacidosis, renal failure with uremia, and ingestion of toxic alcohols such as methanol and ethylene glycol. Salicylates are another important cause.
How does albumin affect the anion gap?
Albumin is a major unmeasured anion in blood. If albumin is low, the anion gap may look lower than it really is. That is why a corrected anion gap is often used in clinical interpretation. It helps uncover acid-base problems that might otherwise be missed.
Which symptoms can high anion gap metabolic acidosis cause?
Common metabolic acidosis symptoms include rapid breathing, nausea, vomiting, fatigue, abdominal pain, confusion, and weakness. Severe cases may cause altered mental status, low blood pressure, or signs of shock. Symptoms depend on the underlying cause and how quickly the acidosis develops.
At what point should high anion gap metabolic acidosis be considered an emergency?
It should be considered an emergency when there is tachypnea, confusion, hypotension, shock, suspected toxin ingestion, severe dehydration, or rapidly worsening illness. An abnormal arterial blood gas or very low bicarbonate can also signal danger. Because the underlying causes may include sepsis, poisoning, or organ failure, urgent evaluation is often necessary.