Understanding the Anion Gap?
The anion gap is a calculated value that helps doctors interpret serum electrolytes and spot less obvious problems in acid-base balance. It is not measured directly. Instead, it is derived from values typically reported on a basic metabolic panel or comprehensive metabolic panel, most often using sodium, chloride, and bicarbonate.
In simple terms, the anion gap contrasts the positively charged ions and negatively charged ions in the blood. Because common lab panels do not capture every ion, the calculation acts as a practical gap-finder for unmeasured acids or other charged particles. That is why the anion gap calculator is often used as a rapid clinical tool during lab interpretation.
The result can provide a useful diagnostic clue when a patient has a potential acid-base disorder. It is especially helpful when serum bicarbonate is low or when a blood chemistry panel suggests a metabolic abnormality. The anion gap value helps distinguish whether the cause of acidosis is likely to be build-up of acids or a loss of bicarbonate with secondary chloride changes.
Although the exact anion gap range changes by laboratory and method, the concept remains the same: if the result is outside the expected reference range, it can suggest a hidden problem in the body’s buffer system.
When an Anion Gap Should Be Checked
The anion gap should be checked when there is concern for metabolic acidosis, especially if the cause is not obvious. It is a reasonable next step in evaluating unexplained acidosis, since it helps identify whether the problem is a high anion gap metabolic acidosis or a normal anion gap metabolic acidosis.
Requesting an anion gap is particularly helpful when a patient has abnormal bicarbonate on a basic metabolic panel or when the https://anion-gap-calculator272.lowescouponn.com/can-potassium-be-included-in-the-anion-gap-calculation clinician suspects an acid-base disorder based on symptoms, history, or other lab results. In these situations, the calculation can quickly focus the differential diagnosis and guide follow-up testing.
The anion gap may also be checked during a broader clinical assessment if the patient has signs of systemic illness, dehydration, altered mental status, or respiratory compensation. Because the result reflects changes in the concentration of major electrolytes, it can reveal a major metabolic derangement even before the full clinical picture is clear.
Common triggers for ordering it include low serum bicarbonate, suspicion of toxic exposure, severe infection, poor perfusion, or worsening renal function. If the initial panel suggests a problem but does not explain why, the anion gap can be the missing piece of the puzzle.
Typical Clinical Scenarios That Need an Anion Gap
Specific conditions frequently lead to an anion gap calculation because they are well-known causes of metabolic acidosis. Such conditions often involve extra acid formation, decreased acid removal, or ingestion of substances that affect blood chemistry.
Diabetic ketoacidosis is one of the best-known examples. In this case, ketone accumulation raises the anion gap value and produces a classic high anion gap metabolic acidosis. The result can aid in confirm severity and monitor improvement alongside glucose and ketone testing.
Lactic acidosis is an additional major indication. When tissues are underperfused or the body is under severe physiologic stress, lactate can rise and raise the anion gap. This is often observed in sepsis, shock, hypoxia, or additional serious illnesses that require urgent care.
Kidney failure is also a common reason to check the anion gap. When the kidneys cannot remove acids effectively, unmeasured anions can collect in the blood. In late-stage renal impairment, the anion gap may rise and signal worsening metabolic imbalance.
Toxin ingestion is a key use case. Poisoning with substances such as salicylates, ethylene glycol, or even particular patterns involving acetaminophen use can lead to dangerous acid-base changes. In these cases, the anion gap can act as an early warning sign of toxic ingestion and should be interpreted promptly in context.
Because the clinical picture can evolve rapidly, the anion gap is often ordered alongside other blood chemistry tests to support real-time decision-making.
How an Anion Gap Calculator Is Used
An anion gap calculator makes easier a calculation that is often part of standard lab interpretation. Clinicians enter the relevant electrolyte values, usually from a basic metabolic panel or comprehensive metabolic panel, and the tool generates the result immediately.
Most commonly, the calculator uses sodium, chloride, and bicarbonate. Since the result depends on those exact numbers, the calculator is only as reliable as the labs used. A small change in any one of those values can affect the outcome, especially when the numbers are anion gap clinical significance already near the edge of the expected range.
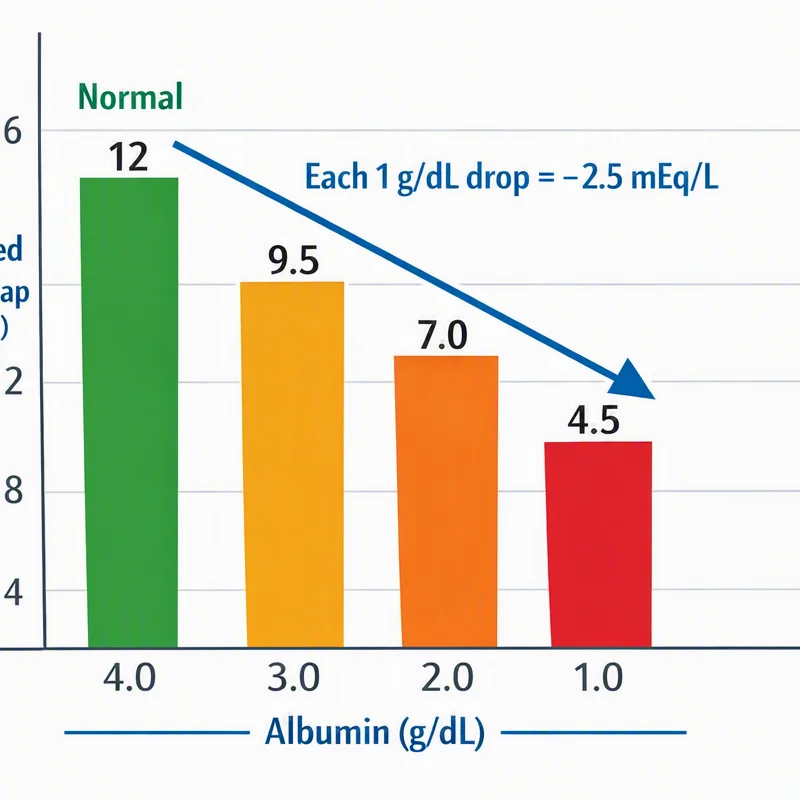
One important feature is albumin correction. Because albumin is a major unmeasured anion, hypoalbuminemia can make the anion gap appear falsely normal or low. A corrected result can therefore be more informative than the raw value. The corrected anion gap is particularly useful when evaluating acidosis in hospitalized patients or anyone with low protein levels.
The calculator also supports interpretation of serum bicarbonate changes by connecting the electrolyte pattern to a likely acid-base process. This makes it easier to decide whether a patient’s findings reflect metabolic acidosis, another acid-base disorder, or a mixed problem that needs more testing.
In practice, the tool is not a diagnosis by itself. It is a systematic way to support clinical assessment, support a suspicion, and prompt the next step in workup.
High Anion Gap vs Normal Anion Gap
A high anion gap typically suggests that undetected acids are accumulating in the circulation. This pattern is often seen in high anion gap metabolic acidosis, where the body is retaining acids more quickly than it can remove them. Frequent causes include ketoacidosis, lactic acidosis, kidney failure, and toxin ingestion.
A normal anion gap does not rule out acidosis. Instead, it may point toward normal anion gap metabolic acidosis, also called hyperchloremic acidosis. In this pattern, bicarbonate is depleted and chloride rises to maintain ionic balance. This can occur with gastrointestinal bicarbonate loss, certain kidney tubular disorders, or other processes that lower serum bicarbonate without increasing unmeasured anions.
It is also important to remember that not every acid-base change means acidosis. A patient may have a mixed disorder in which the anion gap is altered alongside metabolic alkalosis. For example, vomiting, diuretic use, or volume depletion can affect the overall picture and complicate lab interpretation.
Recognizing the difference between a elevated anion gap and a typical anion gap helps clinicians decide which disease processes are more likely and which tests should come next. In other words, the value is not just a number; it is a map for assessing the body’s current acid-base state.
What Can Change the Result?
Multiple factors can affect the measured anion gap and should be taken into account before making conclusions. One of the main is hypoalbuminemia. Because albumin holds negative net charge, low albumin can lower the measured anion gap and hide an hidden acid problem. That is why albumin correction matters so much in real-world lab interpretation.
Lab error is another potential problem. Specimen handling problems, analyzer variation, or transcription mistakes can all lead to misleading numbers. If the result does not match the clinical picture, repeating the chemistry panel may be appropriate.
Changes in pH can also affect interpretation. The anion gap itself is not a direct pH measurement, but it is part of the overall acid-base assessment. If the patient has significant acidemia or alkalemia, the rest of the workup may need to include gas analysis and repeat chemistry to clarify the full pattern.
Potassium is sometimes included in an alternate form of the calculation, though many routine versions do not use it. Even when it is not part of the formula, shifts in potassium can still matter because they often accompany a larger electrolyte imbalance. In short, the anion gap should always be interpreted alongside the rest of the blood chemistry and the patient’s symptoms.
When to Seek Further Testing or A Medical Review
An abnormal result often calls for further assessment rather than a final conclusion. If the anion gap is elevated, or if unexplained acidosis remains, clinicians may order an arterial blood gas to better define the acid-base status and respiratory compensation. This is especially useful when the severity of illness is not obvious or when there may be a mixed disorder.
Repeat testing is also advisable when the result is unexpected, inconsistent with the clinical picture, or potentially affected by sampling issues. A repeat chemistry panel can confirm whether the abnormality is still present or temporary.
Newly developing or worsening clinical symptoms should always guide urgency. Symptoms such as confusion, vomiting, rapid breathing, marked weakness, dehydration, or declining mental status may indicate a more significant underlying process. In that setting, the anion gap is just one piece of a broader evaluation.
Because an abnormal value can reflect a important electrolyte imbalance or serious metabolic abnormality, the result should not be ignored if it matches the patient’s condition. Instead, it should trigger timely evaluation of renal function, toxic exposure, lactate, ketones, and other relevant studies.
Frequently Asked Questions
What is the usual anion gap range?
The anion gap normal range depends on the laboratory method and whether the calculation includes potassium. Many labs report a limited range, but the exact reference range can vary. Always interpret the result using the lab’s own reference range rather than relying on a single universal number.
When should the anion gap be checked with lab tests?
It should be ordered when there is concern for metabolic acidosis, an acid-base disorder, or unexplained acidosis. It is especially useful if the basic metabolic panel or comprehensive metabolic panel shows low bicarbonate or if symptoms suggest a hidden metabolic problem.
What makes the anion gap significant in metabolic acidosis?
It is used to identify the reason of metabolic acidosis. A high anion gap suggests accumulation of unmeasured acids, while a normal anion gap points toward bicarbonate loss with chloride replacement. That distinction guides the next steps in evaluation and treatment.
Does low albumin change the anion gap result?
Yes. Hypoalbuminemia can reduce the measured anion gap and mask an abnormality. That is why albumin adjustment or albumin correction is necessary when reviewing results, especially in hospitalized or critically ill patients.
How should it be handled if the anion gap is high?
A high result should trigger assessment of the full clinical picture and consideration of causes such as diabetic ketoacidosis, lactic acidosis, kidney failure, or toxin ingestion including salicylates and ethylene glycol. Depending on the scenario, clinicians may request an arterial blood gas, repeat testing, and additional labs to assess the source of the acid-base disturbance.